





$VKTX - Oral VK2735 is positioned to be the first oral GLP-1/GIP dual agonist on the market‼️
The SUNRISE oral Phase 3 program targets only ~1,120 patients across two trials (560 each). That is roughly a quarter of the ~4,700 Lilly enrolled in ATTAIN-1 and ATTAIN-2 for orforglipron. 🤔
The smaller program is likely possible because oral VK2735 is the same molecule as SC VK2735, so it can lean on the VANQUISH safety database (~5,500 patients).
This should let oral VK2735 reach market at a fraction of the incremental R&D cost of new-molecule SMOL single agonists like orforglipron.

$VKTX ORAL VK2735 represents the most advanced oral dual GLP-1/GIP agonist in clinical development and has the potential to be positioned as either an induction therapy or in the maintenance setting, increasing the treatment options available to patients and clinicians
$VKTX - There was only 1 (as in ONE) discontinuation due to an AE in the induction phase of the Maintenance trial per the PR*. ONE, in an accelerated 2-week induction titration scheme‼ (I'm not talking about total DCs in induction, only the ones due to AEs.) For those of you good at math one out of ~161 treated in induction is less than 1%.
Discontinuations for other reasons (e.g., withdrew consent, lost to follow-up, protocol deviation) aren't reported, but the n's suggest they happened. There were 161 VK2735 subjects in the induction efficacy population and only 143 appear in the maintenance arms, so roughly 18 appear to have left during induction (I did the math).
➡I will repeat for clarity that only 1 (one) discontinued due to an adverse event out of 161 treated in induction. That is less than 1%. (@ChillBanking please feel free to comment😉)
➡This was in what many thought was a really aggressive titration scheme that would be problematic (not me, and certainly not Viking).
➡On GI AEs during induction, the PR says they were "characterized as mild" and that the incidence "was low and declined over time." Despite "the accelerated 2-week titration schedule," rates were "similar to those reported in the prior Phase 2 study" (VENTURE), "which utilized 3-week titration steps."
*Note: Here is the direct quote from the press release I refer to: "One subject (1%) in the induction period discontinued VK2735 treatment due to an adverse event."
$VKTX Upcoming major catalysts in next 9 months :
➡️Phase 3 Oral VK2735 start
➡️"Obesity Week"-> Detailed data on Maintenance Study
➡️VK3019 Viking's Amylin compound reporting on ph1 (SAD data could come before EOY)
➡️ Oral Maintenance study. Should include a QW dosing option and this remains the first ever dual agonist Oral in development.
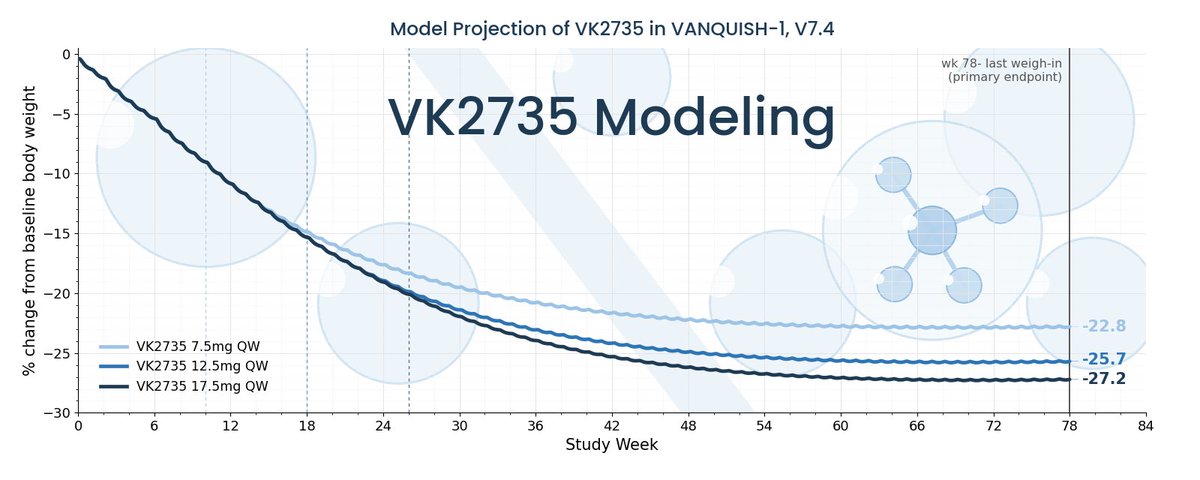
➡️VANQUISH-1 ph3 Top line data (study should complete May 2027)
Don't sleep on the Oral. The Amylin has great potential. VANQUISH-1 Phase 3 reporting is not that far away and the most important data set for Viking.
$VKTX Maintenance results out today were exceptional and a real best case IMO. I will have a lot more to say later but here are a few choice comments:
➡️WL is BIC. VK2735 is better than RETA at same point in time. It's just better with far fewer side effects.
➡️Monthly (QM) dosing works in maintenance
➡️Every other Week (QOW) dosing works in maintenance.
➡️No evidence of Plateau out to 33 weeks.
➡️Tolerability is great even at accelerated dosing and we have some YADOs (Yet Another Dose Option).
➡️We now have data beyond 13 weeks,. We have data to 21 weeks in a very high powered pool arm that should remove a lot of risk for Big Pharma to make a move before EOY
😊😊😊This was simply a home run IMO. 😊😊😊


MS notes "we believe some investors may be focused on the 17.5mg weekly arm through the full 33 weeks to gauge the longer-term weight loss profile". ⚠️⚠️⚠️⚠️A warning on this⚠️⚠️⚠️⚠️:
➡️N=15 in this arm, and it's the same 15 people who are inside the N=120 pooled induction cohort. They're measured precisely at week 21, then become a small subgroup for the next 12 weeks. A couple of discontinuations- and whatever assumption gets made about where those people ended up- can bend the curve on its own.
➡️A plateau at N=15 may not be a real plateau. My rough math- roughly about ±4 percentage points on the mean at 95%, so a −22% print is really "somewhere between −18% and −26%."‼️Did I say N=15 enough here?
➡️This arm stays on 17.5mg the whole 33 weeks- the dose doesn't drop. But 12 of those weeks sit inside a "maintenance phase" where most other participants are being stepped down or placebo'd. I think that biases the whole period toward maintaining rather than continued aggressive WL. That's my hypothesis, not a known. Just be aware this data may be poorly received and wrongly interpreted.
➡️This cohort also sits after 21 weeks of induction, where WL curves tend to flatten anyway.
The stock may react negatively to this arm and violently(don't shoot the messenger). Modeling says continued WL, not a plateau- but N=15 is noisy enough that a flat-looking curve could be sampling. It could also print great. Either way it's 15 people, healthy adults on a compressed titration in a PH1, not a VANQUISH preview.
👉👉👉The much more important number is WL% at week 21, where N=120.👈👈👈
$VKTX MS Ph1 VK2735 maintenance data this month Catalyst Importance: Very High. Catalyst Surprise: Meaningful upside surprise
• Ph1 VK2735 data (injectable: monthly and Q2W) in weight maintenance are
expected in 3Q26 and oral maintenance data are expected 1H27.
• Data from an exploratory oral cohort in Ph2 suggests potential as a maintenance
therapy and provides positive readthrough to the injectable formulation.
• Induction phase designed to maximize early weight loss with an aggressive titration
schedule and thus does not provide read-through on the tolerability profile.
• Expect focus on safety during the maintenance phase given theoretical increased
risk of GI events, while we view <20% vomiting as acceptable.
• Beyond maintenance, we believe some investors may be focused on the 17.5mg
weekly arm through the full 33 weeks to gauge the longer-term weight loss profile
of VK2735 compared to approved or other treatments in development.
• We believe flat or continued weight loss during maintenance could drive +25-30%
upside. While a sharp rebound (≥5% weight regain) may pressure shares (-10-15%).
$VKTX - @bioinvestor24 makes excellent points in the quoted post. 🙏 I agree with all of them, and want to add detail on one:
➡️ The +5 mg step at Week 10 in #VK2735 VENTURE (10 → 15 mg) did not produce an outsized AE signal. The Week 1 spike in that arm came from a 5 mg opening dose in drug-naive patients. This is the only arm that started there. The other arms opened at 2.5 mg.
➡️ 15 mg arm, Week 1: 27 GI events, nausea in 17 of 35 (48.6%). Week 10: 4 GI events total - nausea 3 (8.6%), vomiting 1, no diarrhea, no constipation. A real uptick, but not a Week 1 repeat and gone by Week 11.
➡️ This isn't unique to a step-up week. The 5 mg arm logged 12 GI events in Week 4; 5 mg Week 2 and 10 mg Week 4 logged 6 each.
➡️Small scattered clusters show up throughout the study.
Caveats: n=35 per arm, so one patient moves a rate ~3 points, and by Week 10 that arm is already tolerized.
Here are some slides including a modified one from my original article (green = the nuance). Take a look for yourself:


One observation in $VKTX phase 2 from 2024 is the broad wt loss across population. At 15 mg dose 100% lost > 5% and 89% lost > 10% in 13 wks.
There were 35 pts in this arm and 7 DC drug for whatever reason ( 28 finished the study on drug ) . But 31 pts lost > 10% .. and 35 lost > 5%
it shows that pts didn’t stop early .. there was 10 to 15 mg step up that made a few pts uncomfortable which VK is avoiding in all subsequent studies.
When I look at $PFE Vesper 3 with 24% vomit ( double $LLY TZP) and 20% DC from any reason , I wonder how they will be able to combine with their amylin ( 37% vomit in MAD) ? No wonder they new phase 2 B is like 900 pts as ptiabaky still can’t figure the right combination doses despite doing 200 pt trial in 2025-26
Same issue will face $ABBV if they end up relying on amylin combination with any future asset. And $RHHBY ..
and $NVO is doing now 7.2 mg sema / CagriSema trial 😂
Knowing that a number of pts are de escalation due to excessive wt loss on VK2735 and $LLy retatrutide trials .. not sure if combinations will have serious role in future… or be competitive with excellent single agent approaches


$PTGX is on a roll‼️ Just got approval for another partnered peptide drug. MIMRYLO (aka rusfertide) was approved Aug 28. They got a best-case "broad and clean label" according to JPMorgan.
➡️As a result, Protagonist got another big milestone payment ($275M) and will receive double-digit pure profit royalties on this second drug with blockbuster potential (ICYMI - ICOTYDE was the first).


4
1,123

$VKTX - The GI profile in the induction phase matters even though it is not the same as the titration in Vanquish. If it is good (as in consistent with the class and equal/better than say Tirzepatide's) then VK2735 will have another way to dose -> 2-week titration blocks rather than 4. Yes, this would be "off-label" but there is a lot of that happening now with both approved and compounded GLP1s varieties.
Consider also:
➡️There is a segment of the market that will want to lose weight fast and would possibly risk the AE profile to do it. Getting to the top dose of 17.5mg in 12 weeks (the time it takes in induction) rather than 26 weeks would also save them money as an incentive.
➡️This would be a material competitive advantage over Tirzepatide should this 12-week titration prove viable. (Tirzepatide takes 20 weeks to get to its top dose of 15mg)
➡️ Being able to titrate up quickly says something about VK2735 tolerability that reads through to the Ph3 Vanquish study in a positive predictive way.
VK2735's TMax at 70-90h is later/longer than key other GLP1's (E.g. Tirz, Reta, Sema, etc.) . It is a big reason VK2735 is likely to succeed in the Maintenance Trial with 2 week titration blocks IMO.
@Doctor_Salomon @semodough @pharmdca @GilaMonstrum


$VKTX
Would not pay attention to GI profile from induction phase of the ph2 maintenance study. It’s almost a waste of time since the GI AEs from phase 3 (what matters) likely to be lot lower given the slow titration.
The GI AEs from the maintenance DO matter since they have read thru to EOW or monthly dosing. Monthly dosing is a bit ambitious IMO but if GI AEs are low, it becomes really attractive.
$VKTX - RJ Fireside chat main points (along with RJ notes in parens) along with my translation in bold:
➡️Best-in-class dosing flexibility (Subq could be QW, QOW or QM, Oral could be QD or QW) #VK2735 has 5 realistic dosing options ‼️
➡️Maintenance is a key market in obesity (it is easy to
start patients, but hard to keep them on drug for >1 year for reasons such as cost, inconvenience,
or tolerability.) Viking has BIC tolerability and an organizationally lean corp structure that will lead to a very competitive cost position.🤔
➡️Management is looking for retention of at least ~75-80% of weight loss achieved at Week 21 (BL typically "under promises") VK2735 is likely to do better than this‼️
➡️Readthrough from competitor datasets (VKTX doesn’t consider any of the recent readouts to be “game-changers” thus far, and thinks the tirzepatide/eloralintide dataset coming at EASD later in October is key) BL thinks that the VK2735/VK3019 combo is going to be Vikings second "game-changer."🤔
➡️CordenPharma manufacturing deal is massive and expandable. (The deal with CordenPharma (announced last year) is a multi-ton API capacity
deal allowing for 100M autoinjector units, 100M vial and syringe units, and 1B tablets, that is expandable at Viking’s option. VKTX has now added
two additional API suppliers in the multi-ton range, and will be adding a third supplier soon (four total), and they are also working on back-ups for the fill and finish as well as an added safety net.) There is no big pharma manufacturing moat when it comes to peptides. Viking will not be capacity limited at launch or in the future‼️
➡️Thoughts on commercial competitor readthrough and the bar in the oral program (Management maintains the subQ market will remain the dominant market...estimated 80-20 or 75-25 split...the oral Wegovy uptake was much stronger than expected ) The SubQ market is the main TAM. Secondly- the idea that not being able to fast for 30 mins in the AM on the oral is a problem is ridiculous for people trying to lose weight especially considering the drug suppresses your appetite. 🤔
➡️VK3019 emerging as potentially both a monotherapy and combo therapy. (VKTX initially viewed the VK3019 amylin program as more of an addon to VK2735, which could potentially increase weight loss from the ~20% range to the ~30% range) VK3019 may be a blockbuster all by itself‼️

RJ: $VKTX $118 PT
Best-in-class dosing flexibility is key to Viking's strategy. VKTX aims to create best-in-class therapeutics with best-in-class dosing flexibility for patients on the metabolic space. They could have the first dual-agonist with both oral and subQ flexibility.

$ALT - Alt's pemvidutide PERFORMA study initiated Aug 3, 2026. Cohort 1 is ~990 biopsy patients, Cohort 2 ~800 NIT patients and Alt optimistically IMO expects a data readout in 2029. The best case approval is 2030 and more likely 2031. Of note:
➡️ALT's PERFORMA study is very similar to $MDGL's registrational MAESTRO trials for Rezdiffra. Both required biopsies 990 subjects in PERFORMA vs 1,759 in MAESTRO so that was less but still a significant part of the study so PERFORMA requirements were lighter. Alt has raised ~$300M in 2026 and most of that is to fund this trial.
➡️$MDGL has to be pleased with this as it is very costly and takes a long time to get a MASH indication. These are the likely main reasons why $VKTX hasn't gotten any takers on advancing #VK2809 to ph3.
⁉️On the other hand, it is surprising to me that Alt was able to raise the amount of cash that they did for a GLP1-Glucagon based molecule against a backdrop of so many other GLP1 based MOAs already here or coming out that have positive effects on MASH (Sema, Tirz, Reta, Survodutide, and VK2735). So maybe there is still some interest in a "liver directed" MOA like VK2809? I think it is a low probability for Viking to partner the VK2809 THR-β asset but it is not out of the question as clearly there is real interest in new MASH drugs still.

$ALT Initiates PERFORMA Phase 3 Trial of Pemvidutide in Patients with MASH globenewswire.com/news-relea…

3
10
2,326
$VKTX $NVO $LLY $KLRA $PTGX - Bachem announced a new major agreement to supply a large volumes of peptides to an undisclosed partner who has committed to pre payments and long term production‼
➡Even more significant is that they also announced plans to invest $615M USD for a new Swiss based greenfield plant with commercial production starting in 2030. This plant is targeted for high volume mfg.
➡Clearly new greenfield peptide production (probably for the oral peptides?) is needed and large investment is being made in cGMP facilities in Europe.
➡ IMO it is likely that this new production will employ mostly tag based peptide manufacturing which dramatically reduces costs vs SPPS
➡$BANB.SW was up 10% on this news
bachem.com/articles/news/ad-…


$VKTX - Brian Lian has stated on several occasions that the preclinical data for WL on VK3019 - Viking's DACRA) gets WL% that exceeds VK2735 which is very impressive.🤔 Viking has likely tested VK3019 in combo with VK2735 in preclinical models as BL has hinted that a combo study is likely after the ph1 VK3019 trial.
▶ I would expect Viking to finally go after a T2D indication in addition to Weight Loss with the combo compound and take on $LLY's tirzepatide/eloralintide combo which has shown great promise in ph2.
$VKTX Preclinical data from Viking's internally developed DACRAs showed impressive effects on body weight, food intake, and metabolism in healthy rats and diet-induced obese (DIO) mice compared to control-treated animals. Results showed Viking's DACRAs reduced food intake in lean rats within 0 to 72 hours after a single dose. At 72 hours, these compounds reduced body weight by up to 8% compared to controls.

