

T, B, & NK cells and Stem cell scientist for 50 yrs , Commercialized CD4/IL-2r, CD34 Mabs at BDMC &ABI TaqMan mRNA Gene Expression during human genome project.
California
Joined September 2010
- Tweets27.1K
- Following948
- Followers1.2K
- Likes46.8K




Andy Blidy retweeted

$NWBO #HIV #DCVax #DendriticCells #Immunotherapy
𝗧𝗵𝗲 𝗴𝗼𝗮𝗹 𝗶𝘀 𝘁𝗼 𝗲𝗻𝗱 𝘁𝗿𝗲𝗮𝘁𝗺𝗲𝗻𝘁 𝘄𝗶𝘁𝗵𝗼𝘂𝘁 𝗹𝗼𝘀𝗶𝗻𝗴 𝗰𝗼𝗻𝘁𝗿𝗼𝗹 𝗼𝗳 𝗛𝗜𝗩.
HIV medicines suppress the virus. Silent infected cells can remain behind and restart it when treatment stops.
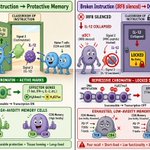
Kalinski and Mailliard’s type 1 dendritic-cell approach, called αDC1, addresses that hidden infection through the immune system’s own instructors.
𝗘𝘅𝗽𝗼𝘀𝗲 𝘁𝗵𝗲 𝗶𝗻𝗳𝗲𝗰𝘁𝗶𝗼𝗻. 𝗣𝗿𝗲𝗽𝗮𝗿𝗲 𝘁𝗵𝗲 𝗮𝘁𝘁𝗮𝗰𝗸. 𝗠𝗮𝗸𝗲 𝗰𝗼𝗻𝘁𝗿𝗼𝗹 𝗹𝗮𝘀𝘁.
In patient-derived laboratory cultures, prepared dendritic cells helped bring latent HIV into view. In separate experiments, dendritic cells presenting HIV fragments generated killer T cells that attacked infected targets and suppressed infectious viral outgrowth.
Those are real biological components of an HIV-cure strategy. Lasting control in people is the clinical goal.
The new JCI Insight paper takes the next question inside the vaccine: which cells supply its strong immune instruction, and how can that function be made more consistent?
The αDC1 preparation produced substantially more active IL-12 than the PGE2-matured comparator. The small percentage of cells detected making IL-12 is a laboratory measurement of one function, not a patient response rate.
𝗧𝗵𝗲 𝗮𝗶𝗺 𝗶𝘀 𝗱𝗲𝗽𝗲𝗻𝗱𝗮𝗯𝗹𝗲 𝗽𝗼𝘁𝗲𝗻𝗰𝘆, 𝗯𝗮𝘁𝗰𝗵 𝗮𝗳𝘁𝗲𝗿 𝗯𝗮𝘁𝗰𝗵.
That is where Northwest’s Kalinski-related licenses and αDC1 manufacturing work matter. The company is building the production and clinical-development capabilities needed to turn these cell designs into reproducible medicines.
The full article connects the HIV findings, helper-cell licensing, IL-7 support and Northwest’s manufacturing role around that single purpose: immune control that outlasts treatment.
𝗙𝘂𝗹𝗹 𝗮𝗿𝘁𝗶𝗰𝗹𝗲 ↓
teapaw.org/andrewcaravello/articl…

$NWBO
Type 1-polarized DC immunotherapeutic contains heterogeneous populations with IL-12p70 production restricted to a rare subset
insight.jci.org/articles/vie…
This paper compares two types of DC vaccine: αDC1 and PGE2-DC (pgDC). Dr. Kalinski is one of the authors.
Here’s the really interesting part. Both vaccines were also tested head-to-head in a clinical trial — not in cancer, but in HIV (DC-HIV04, NCT03758625).
So if you think DC vaccines can only treat cancer, think again.
Comparison of Dendritic Cell-Based Therapeutic Vaccine Strategies for HIV Functional Cure (DC-HIV04)
clinicaltrials.gov/study/NCT…
Comparison of Dendritic Cell-Based Therapeutic Vaccine Strategies for HIV Functional Cure
reporter.nih.gov/search/y6Bu…
Autologous Dendritic Cell Vaccine in HIV1 Infection
clinicaltrials.gov/study/NCT…


Andy Blidy retweeted

$NWBO’s DCVax-L UK application seeks approval for both newly diagnosed and recurrent glioblastoma. My view: that scope deserves attention—patients need options at both stages. MHRA review continues. #DCVaxL #Glioblastoma


Andy Blidy retweeted

To cure cancer you need SenoMune...and NK cells
Melanoma stem-like cells can recruit monocytes and reprogram macrophages into an unusual inflammatory, pro-angiogenic state. These macrophages then suppress NK-cell cytotoxicity. A 2026 study reveals another mechanism by which cancer stem cells manipulate immunity.
doi.org/10.3389/fimmu.2026.1…

Andy Blidy retweeted

$nwbo @alphavestcap
teapaw.org/andrewcaravello/status…
@andrewcaravelloDCVax-L, Braelyn and Stephen Moore’s Challenge to the FDAWhat Stephen Moore Is Asking For
0:00 / 9:59]Stephen Moore has called on the FDA to let Americans access promising cancer treatments at home. His October 20 commentary at Rasmussen Reports,“The FDA Should Grant Americans the Right to Try New Cancer Treatments,”opens with a young woman traveling from South Carolina to London for personalized immunotherapy. The patient is Braelyn. Her treatment is DCVax-L. Her mother, Amanda Hollensbe, publicly identified her as the subject of Moore’s column. [1,3,4]Moore asks for three changes: let rare-disease patients try treatments supported by a compelling prospect of success; broaden compassionate use so a physician and informed patient can proceed through notification to FDA; and allow American access to qualifying therapies approved in developed nations under a separate designation. His argument places the treatment decision, and the cost of waiting, directly in the national policy debate. [4The objective is a usable American pathway for DCVax-L. That requires a clear answer to a family’s immediate access request, a complete clinical and manufacturing case for FDA assessment, and treatment centers prepared to provide care with costs understood in advance. Moore’s intervention should lead to named responsibilities and a published process that physicians can use. The result to pursue is an eligible patient receiving treatment through an organized U.S. clinical service.]The institutional connection gives that intervention weight. Moore cofounded and chairs Unleash Prosperity. With health economist Tomas Philipson, he coauthored a February report on the economic value of reducing cancer deaths and an FDA-reform report dated May. The latter proposes advancing regulatory review, manufacturing preparation and payer coverage work together, and explicitly names glioblastoma among its targets. His new column brings a patient’s experience into a reform agenda already written down. [11,26,27]Braelyn is nineteen and wants to become a Child Life Specialist, helping children through frightening hospital experiences. She has experienced that world from the patient’s side. Amanda describes seizures, difficulty speaking and numbness beginning the day after Braelyn’s sixteenth birthday. Surgery, radiation, infections and rehabilitation followed. Braelyn graduated from high school in May 2025 and started college. [1]Her family travels approximately four thousand miles for an injection appointment that takes minutes. She receives DCVax-L through a special-access arrangement in London. [1]Her vaccine has already been made. In an October 18 public update, Amanda said eight years’ worth of doses had been manufactured from Braelyn’s tumor, with treatment planned over at least the next three years. The family is raising money to reach medicine prepared specifically for her. [2]The MRI sequence is part of the story. The February 26, 2026 image preceded UCLA surgery. Amanda identifies the comparison image as an August scan and reports that UCLA could see no tumor tissue, including residual tissue deliberately left at surgery. In her October 13 updates, she placed that clear MRI after the first three DCVax-L injections and said Keytruda was added afterward. [28,29,30]FIGURE 1. Braelyn’s MRI timeline. The earlier photographed view is undated. The image dated February 26, 2026 precedes UCLA surgery and DCVax-L; the August image follows surgery and the first three doses, according to Amanda’s public account. She reports no visible tumor tissue, including the residual tissue left at surgery, and places Keytruda after the clear MRI. Images supplied by Andrew Caravello. Identifying overlays removed; scan content retained. [28,29,30
]Moore reports clear scans and a young woman attending college. His challenge now concerns where American patients can receive promising care and who can make that decision. The work that follows is concrete: assess the evidence, establish a usable domestic route and prepare the supplier, clinic and payment arrangements together. That is how his three proposals become treatment a family can reach. [4Why Stephen Moore’s Involvement Matters]Moore has spent his career moving economic arguments into public policy. He founded and led the Club for Growth from 1999 to 2004, then served as a senior economics writer and editorial-board member at The Wall Street Journal from 2005 to 2014. Unleash Prosperity’s current biography identifies him as a senior policy adviser to Donald Trump in both 2016 and 2024. [5,27]In 2015, he joined Steve Forbes, Larry Kudlow and Arthur Laffer in launching the Committee to Unleash Prosperity. Its mission centers on economic growth and opportunity, with regulatory policy among its main concerns. The organization identifies Unleash Prosperity Now as its 501(c)(4) partner. The latter publishes the research that gives this story its institutional significance. [6,7,8]Rasmussen Reports, which published Moore’s commentary, is the polling and media company founded by Scott Rasmussen in 2003. Its role here is to carry the argument to a public-policy audience. The economic research and reform proposals come from the Unleash Prosperity organizations. [9That combination matters. Cancer-treatment access has reached a writer and an organization accustomed to asking how rules affect investment, production and opportunity. In that vocabulary, an American invention that patients must travel abroad to receive represents unfinished work: the country has helped create the science without completing the route by which its residents can use it.]The other name to know is Tomas Philipson. The University of Chicago health economist previously advised the head of FDA and then the head of the Centers for Medicare and Medicaid Services, or CMS. He also served on the White House Council of Economic Advisers, including as acting chairman. His experience spans the agency that reviews medicines and a major federal institution responsible for coverage and payment. [10]Philipson and Moore coauthored the reports behind this argument. Their collaboration connects two decisions that families experience as one: whether a treatment can be provided and whether they can obtain it without exhausting their resources. [11,26The Plan Behind The Column]In February 2026, Moore and Philipson published “The Economic Value of Eliminating Cancer.” Their model examines the value of reducing cancer deaths through longer lives, additional productive years and fiscal effects. Its method counts the years a person would otherwise lose. The authors explain that this “implicitly values saving a child more than saving an older person,” because more years of life remain at stake. By that logic, preserving the future of a nineteen-year-old belongs near the center of the economic case for effective cancer treatment. Under its modeled elimination scenario, the authors estimate a present value of approximately $118.5 trillion in 2026 dollars. This is an economic valuation of projected benefits across the population. [26The useful insight is the unit being valued: time to live. A treatment’s price appears immediately on a bill. The value of the life it helps preserve extends through education, relationships, work and ordinary days. That difference helps explain why a narrow accounting of treatment expenditure misses much of what patients and society stand to gain from effective care.At nineteen, Braelyn makes that life-years argument tangible. Successful treatment for a young person can preserve decades in which to study, work, build relationships and help others. Her ambition to work with hospitalized children gives those future years a purpose beyond the figures in a model.]The second report moves from value to implementation. “The Multi-Trillion Dollar Opportunity in Reforming the FDA,” dated May 2026 and prepared by Unleash Prosperity Now, names Moore and Philipson on its cover. It proposes a Cancer Warp Speed Office with oversight across FDA, NIH, the National Cancer Institute, CMS and federal military and veterans’ health systems. Its proposed targets expressly include glioblastoma. [11]The chronology connects the argument. In February, Moore and Philipson valued the years cancer takes. In May, they proposed a federal program and named glioblastoma among its targets. In October, Moore wrote about a young woman with that disease traveling abroad for treatment. [4,11,26]The report’s central operational proposal is to advance scientific review, manufacturing preparation and payer coverage determinations in parallel for designated priority programs. It also calls for more specialist review capacity and clearer disease-specific guidance for external-control studies. [11Read that proposal against Braelyn’s calendar. Her family plans a dose, a flight and a stay in London. A domestic alternative would have to answer three questions together: under what authority can she receive treatment, which institution can provide it and how will it be paid for? An answer to one leaves the family working on the other two.The proposed office would put responsibility for those connections in one place. Reviewers could identify their evidence requirements while manufacturing teams prepare quality records, clinical sites establish procedures and payers assess coverage. The work would advance toward the same practical destination: a patient with an appointment she can keep.That is the connection between Moore’s column and his organization’s program. The column asks for access. The report describes how institutions could be organized to deliver it. The practical test is whether a favorable decision leads to an available appointment, a supplied dose and a payment arrangement the patient can use.Three Proposals, Three Different Decisions]Moore’s first proposal addresses the evidence needed to consider an opportunity. In rare diseases, he argues, a compelling prospect that a treatment could work should support access. Biological understanding and emerging clinical results would carry more immediate weight in a patient’s decision. [4The consequence is to ask a specific question early: what evidence justifies offering this treatment to this patient now? The answer must connect the disease, the proposed intervention, the experience of treated patients and the consequences of waiting. That gives the physician and patient a reasoned basis for action.]His second proposal addresses who can act. Moore would broaden compassionate use so that a physician and an informed patient could proceed through a notification-based arrangement. Responsibility would sit closer to the people confronting the illness. [4]The current American routes explain why that proposal needs precise implementation. FDA expanded access requires agency authorization and institutional review board oversight, with criteria covering clinical need, benefit and risk, and protection of ongoing development. Federal Right to Try uses a different eligibility structure and does not require FDA approval of individual requests. Both require an eligible product and a manufacturer willing to provide it. [12,13A usable reform would tell a family like Braelyn’s whom to contact, which route applies, whether the supplier will participate and where treatment can be given. The answer should include timing and cost. Otherwise, the family is left translating a legal category into a course of care.]Moore’s third proposal addresses which treatments Americans could reach. A qualifying approval in a developed nation would permit domestic access under a designation identifying the treatment’s status. Foreign regulatory work would have a direct consequence for an American patient’s choices. [4]FDA’s Project Orbis already provides an example of shared international oncology review. Partner regulators, including the United Kingdom, can evaluate submissions concurrently while retaining their own decisions and timelines. Moore’s proposal would attach a further access consequence to qualifying foreign authorizations. [14,15]For Braelyn, treatment at home requires a domestic route that accepts her product, a willing supplier and a clinical center prepared to administer it. Moore’s first two proposals address the decisions needed for individual access. His third addresses products with qualifying foreign approvals. Her current care uses a special-access arrangement; bringing that kind of care home requires explicit American eligibility criteria and a participating clinical service. [1,4Together, the three proposals change the threshold for considering access, the authority to provide it and the range of therapies available. Implemented as a connected system, they would give more patients a route through the process before disease takes away the opportunity to use it.Individual Access, Licensing And PaymentA patient’s ability to receive treatment, a product’s marketing authorization and the payment for care are three separate decisions. Making each decision explicit shows what the reform is intended to accomplish.]Individual access answers whether a particular patient can receive an investigational product through an available legal route. FDA’s current guidance describes physician- and industry-submitted requests for drugs and biologics, including individual patients, intermediate-size groups and treatment programs. A usable DCVax-L route must identify which arrangement is appropriate, who will submit the request and whether the manufacturer will supply the product. [31,33]Marketing authorization answers a broader question: whether the product meets the requirements for a defined indication and can be supplied commercially under an approved license. For a cell product, that assessment joins the clinical evidence with manufacturing quality and biological function. The application must support the product and use being requested. [16,23]Payment answers whether the patient can afford the treatment that a physician is able to provide. FDA explicitly advises patients to consider both the investigational product and the medical services required, because private insurance and Medicare often do not cover those costs. A treatment appointment and a funding decision therefore have to be planned together. [34]Braelyn’s family already has an arrangement for treatment in London and is fundraising for its continuation. Bringing care home means building a domestic route for which the patient, product, supplier and clinical site meet the applicable requirements, and resolving how that care will be paid for. A policy should tell the family which of those decisions is settled and who owns the next one. [1DCVax-L Brings The Evidence Question Into Focus]DCVax-L uses two materials from the patient: immune cells collected from blood and material from the surgically removed tumor. Dendritic cells are prepared outside the body and loaded with tumor lysate, the material produced by breaking down tumor tissue. These cells present tumor-derived information to T cells, which are central to an immune attack. The antigen-presenting cell is part of the treatment. [20,21This is why personalized cellular immunotherapy requires both clinical evidence and a reliable manufacturing process. The patient-specific tumor material supplies the targets. The prepared cells have to perform their intended biological work. A manufacturing batch and an immune response are connected steps in the same therapeutic strategy.]Liau and colleagues’ Phase III publication reported statistically significant longer overall survival compared with matched external controls. In newly diagnosed glioblastoma, median survival was 19.3 months from randomization versus 16.5 months. In recurrent disease, it was 13.2 months from relapse versus 7.8 months. Estimated five-year survival in the newly diagnosed analysis was 13.0 percent versus 5.7 percent. [20]Northwest’s July 2026 BNOS presentation reported additional patient-level analyses using propensity-score matching and inverse-probability weighting. These methods adjusted the comparisons for measured prognostic differences. Favorable survival findings persisted in the company’s reported reanalyses of the treated cohort against additional comparator data. [22]This is a concrete reason the external-control question belongs in the access debate. DCVax-L already has published survival findings that require assessment of how the comparator groups were assembled and analyzed. The report coauthored by Moore explicitly calls for clearer guidance in this area. A defined evidentiary route gives developers a target and reviewers a consistent basis for evaluating the submission. [11,20,22For a family choosing whether to pursue a treatment, published results are the beginning of an answer. The clinical record, manufacturing information and safety data must reach the regulator as one organized case. Completing that assessment promptly gives the treating team a decision around which it can organize care.The Plausible Mechanism Pathway And The Voucher Program]Two FDA initiatives address different parts of that task. The Plausible Mechanism Pathway, developed in FDA’s draft guidance as a framework for individualized therapies, concerns evidence. The Commissioner’s National Priority Voucher (CNPV) program concerns the review process. Using them intelligently starts with understanding what each one does. [16,17]FDA’s February 2026 plausible-mechanism draft is built principally for individualized therapies targeting defined genetic conditions in small patient populations. It links a disease-causing abnormality to a treatment, evidence that the target was engaged and improvement in the patient’s clinical course. The draft also says its general concepts may apply to other individualized therapies. [16For personalized cancer immunotherapy, the productive connection is a sequence of measurements. Establish what the cell product is designed to do. Assess that function in the manufactured product. Measure the immune response and follow the disease course. The resulting evidence explains the steps between giving a treatment and observing an outcome. It makes the biological argument testable.]For DCVax, the work is to establish a product-specific evidence plan with the appropriate FDA review division. Mechanistic findings, clinical outcomes, suitable comparators and manufacturing quality belong in that discussion. The framework provides a disciplined way to connect those questions for the therapies within its scope. [16]The voucher pilot addresses how quickly an application can be reviewed. For selected products, FDA targets approximately one to two months and offers enhanced communication and rolling review. Its priorities include unmet medical need, domestic manufacturing and affordability. [17]The short review clock depends on substantial work beforehand. FDA’s FAQ describes advance manufacturing and labeling submissions, generally at least sixty days before the complete application and at least 120 days where foreign inspections are anticipated. A voucher awarded during development can also bring earlier communication benefits. [18That detail changes the practical meaning of speed. The aim is to have the evidence, manufacturing information and inspection planning ready together. A developer pursuing an expedited route must organize the work around that readiness. The time saved comes from earlier preparation and fewer avoidable gaps between decisions.]FDA demonstrated the program’s oncology relevance on October 19, announcing accelerated approval of a new dostarlimab indication for a defined group of patients with locally advanced rectal cancer. The agency described it as the eleventh approval under the voucher pilot, completed nearly four months ahead of schedule, with continued follow-up of the treated patients. [19Braelyn’s next trip is measured in dates on a calendar. That is also how a faster review should be judged: how much earlier can an eligible patient receive an evaluated treatment? Advance preparation gives a favorable decision somewhere to go, through a supplied clinic and an appointment that can be booked.Make Access A Service Families Can Use]For a tumor-derived vaccine, planning begins when tissue becomes available. The surgical and pathology teams should know the requirements for preserving suitable material for a potential cellular therapy, alongside the patient’s diagnostic needs and consent. The treating team needs a clear route for learning whether that material is suitable for manufacture. DCVax-L’s use of the patient’s tumor material makes this an early clinical handoff, long before the eventual injection. [20,21From there, immune-cell collection, manufacture, release testing, transport, storage and administration have to fit the patient’s treatment schedule. The proposal is to make those steps a coordinated service, with a responsible contact and written instructions available to the referring physician.]FDA’s potency-assurance draft connects process design, material controls, in-process testing and release assays to the intended biological activity of cellular and gene therapies. That framework explains why manufacturing readiness belongs beside the clinical dossier: the product supplied to the patient must reliably perform the function being evaluated. [23]The NHS Blood and Transplant collaboration with Northwest and Advent provides a concrete example of assigning parts of the pathway to an established service. NHSBT describes leukapheresis to collect immune-cell starting material and specialist cell processing and handling. Leeds and Oxford are the initial locations, with phased expansion being explored. [24The useful lesson from Leeds and Oxford is that a part of the pathway now has a location and a team. An American program needs the same specificity: where cells are collected, who manufactures the product, who receives it, where the injection is given and whom the family calls when a handoff fails. Those decisions belong in the access program from the beginning.]Payment has to be part of that service. Amanda’s fundraiser estimates about $35,000 for each of seven planned future treatment trips, including the dose, transport, administration, flights and lodging. Her budget puts the full cost of access in one place. [1A domestic program should remove avoidable travel costs and establish treatment charges, coverage and financial support early. A family needs to know what it owes before the appointment approaches. Making the route usable beyond households able to finance international travel is where the reform becomes a change in who can receive care.Who Should Do What Now]FDA and HHS should make early, product-specific engagement the center of the regulatory work. For DCVax-L, the sponsor and the appropriate FDA division should define the clinical evidence to be assessed, the comparator and sensitivity analyses required, the safety follow-up, and the manufacturing and potency information needed. They should also resolve whether concepts from the plausible-mechanism framework fit this product’s proposed evidence strategy. That produces an agreed set of questions and an actionable submission plan. [16,23,25]Northwest and its manufacturing partners should organize the clinical, safety and production records around those questions. The public-facing task is equally concrete: maintain an easily found account of how U.S. physicians can ask about access, the criteria used to evaluate requests, the company’s willingness and capacity to supply treatment, the documents required, the expected response time and the costs. FDA explains that manufacturers create expanded-access programs and that it can also consider individual requests where no suitable program exists. The sponsor’s participation is therefore central to a workable route. [31]Confidential manufacturing information can remain protected while the clinical pathway becomes clearer. FDA describes a Letter of Authorization that permits the agency to reference information in the company’s existing investigational file for a physician’s individual-patient application. This provides a practical way to connect the doctor’s request with the manufacturer’s technical record. Public procedural guidance and confidential product know-how can coexist. [32]Clinical centers should identify the physician responsible for the patient, the team receiving and administering the product, the required oversight and the staff coordinating follow-up. FDA provides Form 3926 and an electronic request route for individual


Andy Blidy retweeted

The acquisition of NeuroAirmid Therapeutics, Inc. along with certain worldwide rights to HUNT1 (hNSC01), a pluripotent stem cell derived clinical-stage neural cell therapy program for the treatment of Huntington's Disease, adds a third clinical stage asset to $LCTX's development pipeline, and aligns with our capabilities in cell manufacturing, process development, and scale-up. The HUNT1 program represents the culmination of decades of research led by Leslie Thompson, PhD, and is currently being evaluated in the #REGEN4HDclinical study at @UCIrvineHealth.
Full article by @UCICove: innovation.uci.edu/news/neur…
#CellTherapy #HuntingtonDisease #RegenerativeMedicine #UniversityofCaliforniaIrvine
@CEO_Culley @CIRMNews @HDSA @HuntingtonSG @hdfcures
Andy Blidy retweeted

That is a very good post. Anyone in the PSC space can say “we’ll scale” alongside a picture of a 80 or 100L reactor, but a big reactor that you can’t feed with enough competent cells is not a solution. You can’t ignore their pluripotency, response to factors, etc.
Islets don’t expand as easily as some other cell types. Scale will require a massive number of pre differentiated cells which retain their capacity to become islets. Every division, every media change, every hour of culture you’re increasing the risk of a non-target cell outcompeting your product spec. Deferring these issues means making process changes after generating clinical data (and the process defines the product). “Better from the Beginning” $LCTX
Andy Blidy retweeted
Then why don’t you treat the children with something that is 100% safe and proven effective???? what is wrong with the world?
$NWBO #DCVax #DCVaxForBraelyn #RareCancer #RareDisease #PatientAdvocacy
A voice for every rare cancer in FDA’s Rare Disease Framework. The full DCVax-L and DCVax-Direct essay, companion video, evidence and patient guide.

Andy Blidy retweeted
We are honored to join this journey. New approaches are needed in the “hunt” for an effective therapy. $LCTX.
innovation.uci.edu/news/neur…
Andy Blidy retweeted
$NWBO #DCVax #GBM #SFDA
𝗢𝗻𝗲 𝗣𝗿𝗼𝗱𝘂𝗰𝘁 𝗟𝗲𝗳𝘁 𝗦𝘁𝗮𝗻𝗱𝗶𝗻𝗴
London and Riyadh signed a regulatory agreement this week. It covers rare disease treatments and advanced therapies. It names no product.
It does not need to. Line up the evidence and one product is left.
𝟭. 𝗧𝗵𝗲 𝗯𝗿𝗶𝗱𝗴𝗲
Nov 16 and 17: the heads of the MHRA and the Saudi Food and Drug Authority sign a memorandum of understanding in London. Scope: rare disease treatments, advanced therapies, biotechnology products. Working clauses: product assessment, GMP, product testing, supply chain monitoring. Stated aim: patients with limited therapeutic options.
𝟮. 𝗪𝗵𝗼 𝗻𝗲𝗲𝗱𝘀 𝗮 𝗯𝗿𝗶𝗱𝗴𝗲
Saudi reliance pathways recognize the FDA and the EMA. Not the MHRA. They exclude advanced therapies outright. A product the FDA or EMA has approved does not need London to vouch for it. An MHRA-only cell therapy does.
𝟯. 𝗧𝗵𝗲 𝗲𝗹𝗶𝗺𝗶𝗻𝗮𝘁𝗶𝗼𝗻
Casgevy: approved in Saudi Arabia since January 2024.
Lyfgenia and Zynteglo: FDA-approved, licensed to SPIMACO. No UK leg.
Multikine: Saudi Breakthrough route plus a US trial. No UK filing announced.
Fayuvi: the FDA approved it before the MHRA took the file.
MeiraGTx's LCA4 gene therapy: MHRA-first by plan, no Saudi partner announced.
mRNA cancer vaccines: one Phase 3 win, in melanoma. Unproven in cold tumors, and the MHRA's own rare disease draft sets them apart.
𝟰. 𝗧𝗵𝗲 𝘀𝘂𝗿𝘃𝗶𝘃𝗼𝗿
DCVax-L. A rare cancer. A living cell therapy made one patient at a time. The MHRA its only regulator since December 2023. Phase 3 in JAMA Oncology: 13 percent of newly diagnosed patients alive at five years, against 5.7 percent in external controls.
𝟱. 𝗧𝗵𝗲 𝗰𝗹𝗮𝘂𝘀𝗲𝘀 𝗳𝗶𝘁
GMP: the Sawston plant has held an MHRA commercial manufacturing license since 2023, one that allows export worldwide.
Supply chain: NHS Blood and Transplant joined cell collection and processing in October.
Assessment: one dossier, one regulator, in London.
𝟲. 𝗧𝗵𝗲 𝗦𝗮𝘂𝗱𝗶 𝘀𝗶𝗱𝗲
Aug 5: the Saudi FDA issues a rare disease accelerator. It takes products through Phase 3 that are not yet registered in the Kingdom. It accepts natural history data as an external comparator when a concurrent control is not feasible. The UK is on its list of countries whose GMP certificates and inspection reports it accepts.
Aug 6: Northwest Bio and SPIMACO announce an MOU that would give SPIMACO the Saudi FDA filing.
SPIMACO has a dedicated unit for biological, gene and cell therapies.
Saudi Breakthrough status is open only to products not yet registered with any regulator. A request has to go in before London rules, not after.
At the London summit, the Saudi FDA chief called for faster access to innovative treatments "tailored to their needs," naming rare disease patients and specialized therapies.
𝟳. 𝗧𝗵𝗲 𝗨𝗞 𝘀𝗶𝗱𝗲
2014: DCVax-L receives the UK's first-ever Promising Innovative Medicine designation.
Nov 2025: the MHRA's rare therapies paper says large randomized trials in small populations can be "unfeasible and potentially unethical."
Feb 2026: England's National Cancer Plan gives rare cancers their own chapter and names brain tumours a priority.
March 2026: the Rare Cancers Act orders a review of orphan drug rules for cancer.
Oct 2026: after the Prime Minister meets a brain cancer patient, the government tells the MHRA to speed up its orphan drug review.
𝟴. 𝗧𝗵𝗲 𝗽𝗿𝗲𝗰𝗲𝗱𝗲𝗻𝘁
Casgevy. The MHRA approved it first, on Nov 16, 2023. Saudi approval was announced 54 days later.
𝟵. 𝗧𝗵𝗲 𝘄𝗲𝗲𝗸
Same week in London: the MHRA hosts the ICMRA conference on drug development for small patient populations, and the five Access Consortium regulators agree on a secure platform for work-sharing.
The MHRA has not ruled yet. But the plant is licensed, the Saudi filer is named, the Saudi door is open, and the two regulators now have a direct line.
Remove every product that does not need this agreement. One is left.

#dcvax $nwbo #gbm
MHRA - A significant step forward for international Regulatory Collaboration..
linkedin.com/posts/medicines…
investorshub.advfn.com/board…

Andy Blidy retweeted

$NWBO
Andrew Allen of Adventris Pharmaceuticals, a company that barely has a presentable webpage, said that Moderna’s intismeran autogene and BioNTech’s autogene cevumeran “are fundamentally different products.”
adventris.com/
He forgot to mention what the two have fundamentally in common: both need dendritic cells to mount an anti-tumor immune response.
But the DCs these products rely on are fundamentally different from DCs matured with a specific cocktail.
His message is clear: BioNTech’s failure says nothing about Moderna’s product. Whether his message is convincing is another matter.
Did he notice that Merck and Moderna terminated the trial that included a neoadjuvant therapy arm?
A Study of (Neo)Adjuvant Intismeran Autogene (V940) and Pembrolizumab in Cutaneous Squamous Cell Carcinoma (V940-007) (INTerpath-007)
clinicaltrials.gov/study/NCT…
nature.com/articles/d41573-0…
Although intismeran autogene and autogene cevumeran are both mRNA-based neoantigen cancer vaccines, there are too many differences between them to draw any meaningful cross-programme cancer vaccine conclusions about the opposite outcomes, says Allen.
Melanomas are ‘hot’, immunogenic cancers, whereas most colorectal cancers are ‘cold’ tumours that do not trigger a strong immune response. Intismeran autogene was tested with an immune checkpoint inhibitor, whereas autogene cevumeran was used in colorectal cancer as a monotherapy only after patients had completed a full course of chemotherapy. Merck and Moderna relied on a lipid nanoparticle (LNP) delivery vector that is injected into the muscle, while Genentech and BioNTech used an intravenously administered lipoplex vector.
“They are fundamentally different products,” says Allen.
A Study to Investigate the Novel Agent BNT111 and Cemiplimab in Combination or as Single Agents in Patients With Advanced Melanoma That Has Not Responded to Other Forms of Treatment
clinicaltrials.gov/study/NCT…
In collaboration with Regeneron Pharmaceuticals
BioNTech fades out further work with cancer vaccine prospect in late-stage melanoma setting
fiercebiotech.com/biotech/bi…
A Clinical Trial Investigating the Safety, Tolerability, and Therapeutic Effects of BNT113 in Combination With Pembrolizumab Versus Pembrolizumab Alone for Patients With a Form of Head and Neck Cancer Positive for Human Papilloma Virus 16 and Expressing the Protein PD-L1 (AHEAD-MERIT)
clinicaltrials.gov/study/NCT…
BNT113 Plus Pembrolizumab Misses PFS End Point in HPV16+ HNSCC
targetedonc.com/view/bnt113-…
BioNTech's mRNA cancer therapy misses first goal in head and neck trial
reuters.com/legal/litigation…
A Study to Evaluate the Efficacy and Safety of Autogene Cevumeran With Nivolumab Versus Nivolumab Alone in Participants With High-risk Muscle-invasive Urothelial Carcinoma (MIUC) (IMCODE004)
clinicaltrials.gov/study/NCT…
Sponsor: Hoffmann-La Roche
BioNTech and Roche, the sponsor of the trial, have decided to discontinue the Phase 2 clinical trial (IMcode004; NCT06534983) evaluating autogene cevumeran as an adjuvant treatment in combination with nivolumab compared to nivolumab alone in patients with high-risk muscle-invasive urothelial carcinoma due to the rapidly emerging treatment landscape and shifting standard of care.
The companies will focus on advancing autogene cevumeran in the currently ongoing randomized Phase 2 clinical trials in adjuvant pancreatic ductal adenocarcinoma (“PDAC”) and adjuvant CRC.
A Study of Autogene Cevumeran (RO7198457) as a Single Agent and in Combination With Atezolizumab in Participants With Locally Advanced or Metastatic Tumors
clinicaltrials.gov/study/NCT…
Sponsor: Genentech, Inc.
Autogene cevumeran with or without atezolizumab in advanced solid tumors: a phase 1 trial
nature.com/articles/s41591-0…
A Study to Evaluate the Efficacy and Safety of Autogene Cevumeran (RO7198457) in Combination With Pembrolizumab Versus Pembrolizumab Alone in Participants With Previously Untreated Advanced Melanoma. (IMCODE001)
clinicaltrials.gov/study/NCT…
Sponsor: Genentech, Inc.
ESMO 2025 | IMcode001: autogene cevumeran & pembrolizumab in melanoma
vjoncology.com/video/nfqevsf…
The primary endpoint was progression-free survival. We did not see an improvement in progression-free survival for patients who received the combination versus single-agent anti-PD-1. We saw a numerical advantage for overall survival, which is one of the secondary endpoints, but that wasn’t statistically significant either.
The last thing I’ll say about this study, while we see toxicity from autogene severum, we don’t see any enhanced immune-related adverse effects from the pembrolizumab. So the vaccine has its own tox. The Pembro has its own tox. It’s additive. It’s not synergistic.
A Phase II Clinical Trial Comparing the Efficacy of RO7198457 Versus Watchful Waiting in Patients With ctDNA-positive, Resected Stage II (High Risk) and Stage III Colorectal Cancer
clinicaltrials.gov/study/NCT…
Collaborators: Genentech, Inc.
BioNTech-Genentech cancer vax records more deaths than control in scrapped ph. 2 test
fiercebiotech.com/biotech/bi…

#SITC26 #SITC2026 #DCVaxForBraelyn
$NWBO $MRK $MRNA $BNTX $RHHBY
#DCVax #DendriticCells #CancerVaccines #سبيماكو
𝗧𝗵𝗲 𝗰𝗲𝗹𝗹 𝗺𝗶𝘀𝘀𝗶𝗻𝗴 𝗳𝗿𝗼𝗺 𝗡𝗮𝘁𝘂𝗿𝗲’𝘀 𝗻𝗲𝘄 𝗰𝗮𝗻𝗰𝗲𝗿-𝘃𝗮𝗰𝗰𝗶𝗻𝗲 𝗮𝗿𝘁𝗶𝗰𝗹𝗲 𝗶𝘀 𝘁𝗵𝗲 𝗼𝗻𝗲 𝗥𝗮𝗹𝗽𝗵 𝗦𝘁𝗲𝗶𝗻𝗺𝗮𝗻 𝗱𝗶𝘀𝗰𝗼𝘃𝗲𝗿𝗲𝗱.
Asher Mullard’s Nature Reviews Drug Discovery article, “Cancer vaccine development gets complicated,” asks which targets, patients and combinations will deliver lasting benefit. It never names the dendritic cell.
Yet one of its leading experts, Ira Mellman, was Ralph Steinman’s longtime collaborator. Together, they helped explain how dendritic cells process material, present selected targets and shape the instructions T cells receive.
𝗧𝗵𝗲 𝗮𝗿𝘁𝗶𝗰𝗹𝗲’𝘀 𝗼𝘄𝗻 𝗲𝘅𝗽𝗲𝗿𝘁𝘀 𝗹𝗲𝗮𝗱 𝗯𝗮𝗰𝗸 𝘁𝗼 𝘁𝗵𝗲 𝗺𝗶𝘀𝘀𝗶𝗻𝗴 𝗰𝗲𝗹𝗹.
Personalized RNA vaccines use software to select candidate tumor targets.
𝗗𝗲𝗻𝗱𝗿𝗶𝘁𝗶𝗰 𝗰𝗲𝗹𝗹𝘀 𝗱𝗼 𝗯𝗶𝗼𝗶𝗻𝗳𝗼𝗿𝗺𝗮𝘁𝗶𝗰𝘀 𝗳𝗼𝗿 𝗮 𝗹𝗶𝘃𝗶𝗻𝗴.
They process tumor material, present selected pieces to T cells and supply signals that help direct an attack while maintaining restraint toward healthy tissue.
RNA vaccines work through presenting cells already in the patient. DCVax, from Northwest Biotherapeutics, makes preparing those cells part of the medicine.
DCVax-L brings tumor material to the cells: the patient’s dendritic cells are loaded in the laboratory.
DCVax-Direct brings the cells to the tumor: partly activated, unloaded cells are injected to collect material there.
𝗣𝗿𝗲𝗽𝗮𝗿𝗲𝗱 𝗼𝘂𝘁𝘀𝗶𝗱𝗲 𝘁𝗵𝗲 𝗯𝗼𝗱𝘆. 𝗪𝗼𝗿𝗸𝗶𝗻𝗴 𝗶𝗻𝘀𝗶𝗱𝗲 𝗶𝘁.
Preparation shapes the instructor. After the cells return, helper T cells and dendritic cells reinforce each other through reciprocal licensing. Killer T cells attack. Dying cancer cells release fresh material for another round of presentation.
In the pancreatic RNA-vaccine follow-up, one patient’s vaccine-trained T cells lasted for years. When the cancer returned in the lung, those cells were inside the new tumor.
When the cancer changes, the lesson has to change with it. Durable control depends on that cooperation continuing.
The instructor’s function can be improved in the laboratory. In Northwest’s work presented at the New York Academy of Sciences, selected preparation conditions turned low-producing cells into high producers of certain immune signals.
Three decades of dendritic-cell vaccine research belong at the center of this debate.
𝗧𝗵𝗲 𝘁𝗮𝗿𝗴𝗲𝘁 𝗯𝗲𝗴𝗶𝗻𝘀 𝘁𝗵𝗲 𝗹𝗲𝘀𝘀𝗼𝗻. 𝗧𝗵𝗲 𝗶𝗻𝘀𝘁𝗿𝘂𝗰𝘁𝗼𝗿 𝗯𝗲𝗹𝗼𝗻𝗴𝘀 𝗶𝗻 𝘁𝗵𝗲 𝗺𝗲𝗱𝗶𝗰𝗶𝗻𝗲.
📖 Full X Article
teapaw.org/andrewcaravello/articl…
📖 LinkedIn Article
linkedin.com/pulse/missing-c…
🇸🇦 بالعربية على هوامير
الخلايا المتغصنة والتعاون السعودي البريطاني والتحول في رعاية السرطان.
hawamer.com/vb/hawamer301785…
@aljedai


Andy Blidy retweeted

$NWBO
Do all the trials you would like after you unleash the NWBO platform ..

❤️🙏 ANOTHER MRI. ANOTHER ANSWERED PRAYER!
NO EVIDENCE OF DISEASE!!! 🎉❤️
Today, Braelyn had another brain MRI, and I am absolutely OVERJOYED to share that it once again showed NO EVIDENCE OF DISEASE!
NO CHANGE from her August MRI!
And just FOUR DAYS AGO, on Friday, November 6, Braelyn received her 5th DCVax-L treatment in London! 🇬🇧
I cannot begin to describe the emotions.
After more than three years of fighting this devastating brain cancer, three major brain tumor surgeries, radiation, countless treatments, and more fear than I ever imagined a mother could endure, we are now celebrating another MRI showing NO EVIDENCE OF DISEASE!
I wish I could tell you that the scanxiety gets easier. But it doesn’t. At least not for me.
Every MRI brings back the memories of devastating scans, heartbreaking news, and the terrifying uncertainty of what might come next.
I still find myself holding my breath, praying desperately for those words.
And today, we heard them again.
NO EVIDENCE OF DISEASE. ❤️🙏
My heart is overflowing with gratitude.
To every single person who has prayed for Braelyn, supported our family, donated to help make her treatments possible, shared her story, or simply sent us words of encouragement—THANK YOU!
You have helped carry us through the darkest days of our lives, and you are now helping us celebrate some of the brightest.
And to Northwest Biotherapeutics ($NWBO), the brilliant Dr. Linda Liau at UCLA, and the extraordinary Professor Keyoumars Ashkan at King’s College Hospital—there are simply no words adequate to express our gratitude.
Thank you for your dedication, your compassion, and your determination to bring new hope to patients facing this devastating disease.
Braelyn is 19 years old. She’s attending college. She’s dreaming about her future.
And today, once again, her MRI shows NO EVIDENCE OF DISEASE!
GOD IS GOOD! ❤️🙏
#DCVax #BrainCancer #BraelynsFight #NoEvidenceOfDisease
#DCvaxForBraelyn

Andy Blidy retweeted

You are absolutely right, MP McDonagh. Brain tumour patients cannot afford to wait. It was a pleasure speaking with you at Parliament earlier this month.
Clinical research is essential, but so is ensuring patients can access promising treatments now that have already completed major clinical trials.
DCVax-L offers real hope, and families like ours know firsthand how urgently accessible treatment options are needed.
Thank you for your continued advocacy. 💗
Andy Blidy retweeted
@DrOzCMS @SecKennedy @Siobhain_Mc @MHRAgovuk
Please listen to and follow Dr. Caravello!! You will learn what you’re seeking. He’ll show you the answers you seek for brain cancer (all solid tumors actually)! #DCVax is the way and he’ll explain how!
$NWBO #DCVax #DCVaxForBraelyn #Glioblastoma
Siobhain, please put Braelyn Hollensbe and DCVax-L at the centre of this debate. Sharon Hodgson raised Braelyn’s case in the Commons on 4 November.
𝗣𝗵𝗮𝘀𝗲 𝗜𝗜𝗜 𝗶𝘀 𝗰𝗼𝗺𝗽𝗹𝗲𝘁𝗲. 𝗧𝗵𝗲 𝗿𝗲𝘀𝘂𝗹𝘁𝘀 𝗮𝗿𝗲 𝗽𝘂𝗯𝗹𝗶𝘀𝗵𝗲𝗱.
DCVax-L has completed a 331-patient phase III trial. Its published survival analysis reported five-year survival of 13.0% versus 5.7% in external controls.
Subsequent patient-level propensity-score matching, presented at BNOS, reported median survival advantages of 3.4–6.3 months. A separate weighting method produced directionally consistent findings.
INSIGhT independently tested the external-control approach against known randomized results. Carefully matched external controls reproduced the absence of survival benefit for three experimental drugs. That gives the method a concrete benchmark in glioblastoma.
𝗡𝗛𝗦 𝗕𝗹𝗼𝗼𝗱 𝗮𝗻𝗱 𝗧𝗿𝗮𝗻𝘀𝗽𝗹𝗮𝗻𝘁 𝗶𝘀 𝗮𝗹𝗿𝗲𝗮𝗱𝘆 𝘀𝘂𝗽𝗽𝗼𝗿𝘁𝗶𝗻𝗴 𝗽𝗿𝗼𝗱𝘂𝗰𝘁𝗶𝗼𝗻.
On 8 October, NHS Blood and Transplant announced a collaboration with Northwest Biotherapeutics and Advent BioServices to support DCVax-L production, initially involving Leeds and Oxford.
This is a patient-derived treatment: the patient’s own dendritic cells are loaded with material from that patient’s tumor. The phase III publication described treatment as well tolerated.
CheckMate 143, 498 and 548 failed to improve survival in glioblastoma. Ipi-Glio failed too. WIN-Glio is a separate phase I study testing ipilimumab before standard treatment. Its recruitment, safety and survival reporting should be transparent.
𝗖𝗼𝗺𝗯𝗶𝗻𝗮𝘁𝗶𝗼𝗻 𝗱𝗲𝘃𝗲𝗹𝗼𝗽𝗺𝗲𝗻𝘁 𝗺𝘂𝘀𝘁 𝗮𝗱𝗱𝗿𝗲𝘀𝘀 𝗶𝗺𝗺𝘂𝗻𝗲 𝗶𝗻𝘀𝘁𝗿𝘂𝗰𝘁𝗶𝗼𝗻.
Put DCVax-L at the foundation of that work: prepare the cells that teach the immune response, then test the partners that sustain its attack. Dendritic-cell vaccination and checkpoint blockade address complementary parts of the task.
The UK marketing application was submitted in December 2023. Northwest’s November 2026 filing still describes the MHRA review as ongoing.
What specific issues remain unresolved? Who is responsible for resolving them, and on what timetable? What patient-access arrangements are being prepared alongside the review?
𝗣𝗮𝘁𝗶𝗲𝗻𝘁𝘀 𝗰𝗮𝗻𝗻𝗼𝘁 𝘀𝗽𝗲𝗻𝗱 𝘁𝗵𝗲 𝗿𝗲𝘀𝘁 𝗼𝗳 𝘁𝗵𝗲𝗶𝗿 𝗹𝗶𝘃𝗲𝘀 𝘄𝗮𝗶𝘁𝗶𝗻𝗴 𝗳𝗼𝗿 𝗮𝗻𝘀𝘄𝗲𝗿𝘀.
EVIDENCE
DCVax-L phase III results and safety:
jamanetwork.com/journals/jam…
BNOS propensity-score matching and weighting analyses:
nwbio.com/wp-content/uploads…
INSIGhT external-control reanalysis:
pubmed.ncbi.nlm.nih.gov/4217…
NHSBT production collaboration:
nwbio.com/northwest-biothera…
Current company filing on the MHRA review:
sec.gov/Archives/edgar/data/…
CheckMate 143:
pmc.ncbi.nlm.nih.gov/article…
CheckMate 498:
pmc.ncbi.nlm.nih.gov/article…
CheckMate 548:
pmc.ncbi.nlm.nih.gov/article…
Ipi-Glio:
pubmed.ncbi.nlm.nih.gov/4080…
WIN-Glio registration:
clinicaltrials.gov/study/NCT…
UCLA combination research using its academic ATL-DC vaccine, Hiltonol and pembrolizumab:
clinicaltrials.gov/study/NCT…
Braelyn’s case raised in Parliament:
hansard.parliament.uk/pdf/co…
Andy Blidy retweeted

Or the company could simply say "While we continue to believe that our stock price is being maliciously attacked by bad actors, we will as a company choose to remain focused on continuing to deliver milestone after milestone in anticipation of approval and wide ranging use of DCVAX-L and eventually DCVAX to help cancer patients worldwide."

$NWBO
To all the whining fellas out there, STILL arguing the company is not supportive of the share price.
"We can’t even move" stated about the share price after the last two PR's.
Seriously ... do you really try to sell that as news, after the last 4 years of stock manipulation?
We've had at least a dozen of HUGE, MONSTROUS MILESTONES, which no other small biotech have.
Who TF actually builds their own CDMO and get it to be UKs most licensed of its kind?
Who builds their own automation system, having their own engineers make
Who patents a process that now shuns out competitors from at least a couple of gamechanging features.
Who have build a patent portfolio this size?
Who gets tomorrows super dendritic cells inlicensed for a meager 2-3% royalty.
Who gets donated Advent and +100 employees?
Who hires the immunotherapy director from Roswell?
Who secures britains NHSBT to support manufactoring of DCVax-L?
Not one of these made a dent ... so yeah, lets act bloody surprised for the umptenth time. Put on the "OMG" face and lets turn our collective despair into calling ambulance chasers and chase out LP and the management, because they "don't support the share price".
The last 40 days have been nothing but supporting the share price with EXCELLENT news, that should've supported a parkinson patient in a wheel chair in an Indy 500 race. But no .... IT CAN'T.
And we all BLOODY WELL know why.
Geezus H, out of approval ... we would need a new Trump meme coin, a bought SEC director and 6 men in FDA to support the SP.
