







Justin Andrew retweeted

Periodic reminder that setting the Alaris pump at 999/hr is not a fluid bolus. At that rate, it takes 30 mins to give 500 mL.
(This is not about whose fault it is, just about what a bolus actually means & need for clarification).
This is one of the cooler things I’ve read about recently. Vancomycin *dependent* Enterococcus.
This Post is from an account that no longer exists. Learn more
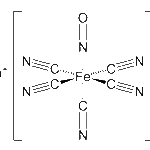
It’s amazing that someone looked at nitroprusside’s structure, a molecular armada of cyanide moieties, and still thought it was a good idea to try it out.

This is true for me. I went from wanting to tube/line every sick patient to having a high threshold for time consuming, uncomfortable, invasive procedures. In the ED, aggressive BPPV/HFNC, large bore IVs (+the occasional IO) and frequent, thoughtful reassessment can do wonders.

Studying for the emergency medicine written board exam is fun because, even in my 9th year of medical training, I am still learning about new things. Today’s example: what a pericardial knock is.
That feeling is your training in action, showing you a red flag you may not even consciously realize is there.
Two relevant maxims were handed down to me in residency: 1) if you’re thinking hard about a scan, do it and 2) the cost of regret is higher than the scan.

Tonight I had two pts, both with vague Sx & nml neuro exams. When my attending asked why I ordered CTs, I didn’t have much of an explanation.. just that I kind of had a bad feeling.
One had edema/midline shift from new mets..
The other had a hemorrhagic CVA.
#TrustYourGut
The honor belongs to a nation deeply grateful for and indebted to your service. Generations of scientists have been and will continue to be inspired by your fine example of scholarship, leadership, and willingness to tackle tough problems.
This Post is from an account that no longer exists. Learn more
ACE inhibitor OD can present as hypotension w/o reflex tachycardia – ?due to ↓baroreceptor sensitivity from ↑endogenous opioids. ACEi inhibit breakdown of enkephalins (δ, µ opioid receptor agonists). Naloxone may rapidly improve/resolve toxicity.
pubmed.ncbi.nlm.nih.gov/3095…

Congratulations to my friend @leilanigilpin, who recently joined UC Santa Cruz’s engineering faculty. She works on making artificial intelligence more accountable, explainable, and ethical — essential qualities for the next generations of AI systems.

Welcome new #BaskinEngineering faculty! 🎉
Leilani Gilpin (@leilanigilpin), assistant professor of computer science and engineering

ALT Leilani Gilpin, new faculty announcement
Congratulations @ahbeeyay and @GeorgeChiampas on this fantastic, timely article detailing how to safely continue sports in the COVID era
This Post is from an account that no longer exists. Learn more
This is essential to safety. Prescribing and dispensing are separate for a reason. MD/DO *can* write for anything, but Pharm is not obligated to fill it, especially potentially dangerous or way off label rx. It is on us to justify to avoid a call or outright refusal… (1/2)
This Post is from a suspended account. Learn more
If you prescribe medications to patients, please read this thread. Anticholinergic effects are common, often poorly recognized, and don’t get better on their own.

Thinking about intubating a patient with hepatic encephalopathy due to depressed mental status? Consider flumazenil, a GABA-A receptor antagonist, first. Possible mechanism: HE-induced upregulation of GABA receptors --> AMS, somnolence
pubmed.ncbi.nlm.nih.gov/3287…
To all who wonder why I push for a PC call for even trivial overdoses/exposures, this is why. Improves patient care, provides continuity if the patient is being admitted, and consults help keep the lights on for the times when you really, really need the help.
You’re unable to view this Post because this account owner limits who can view their Posts. Learn more
Justin Andrew retweeted

It’s getting hot out there, so here’s an annual reminder from your friendly neighborhood ice bath evangelist:
1. Insist on core temperature
2. Cool hyperthermic patients in ice water baths
3. Repeat all summer. Save lives.
Pass it on.
A bittersweet goodbye to the house that built me. 4 years here turned a scared intern into a bonafide ER doc. Thank you for everything @NorthwesternEM.
On to the next chapter with @UCSDHealth.

“‘Adequate MAP’ does not rule out cardiogenic shock” is an essential learning point for everyone who deals with critically ill patients. The body yells when it isn’t perfusing well, one just has to know how to listen.
You’re unable to view this Post because this account owner limits who can view their Posts. Learn more
Everyone about to graduate residency/fellowship and enter academic medicine please read this. Thought process and reasoning matter most. Knowledge gaps are not only ok but expected. And we can always, always, always look up the rest.
