

EM Physician, ECG Enthusiast. I'm here to learn, maybe my efforts can help you do that too.
Burlington, Vermont (UVM)
Joined October 2021
- Tweets3.9K
- Following264
- Followers1.9K
- Likes4.6K









Emerson Floyd retweeted

I made a free website with calipers, annotation, ladder diagrams, and more!
ecgtoolkit.com/
#EPeeps #Cardiology


Emerson Floyd retweeted

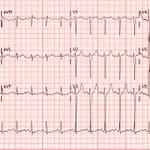
Anterior AMI in patient with WPW. Likely midseptal pathway. Received STK, 98% LAD. Course complicated by heart failure, atrial fibrillation, narrow and wide complex tachycardia, non-responsive to lidocaine, required cardioversion.


Emerson Floyd retweeted

Excellent article about emergency medicine and healthcare: “Emergency medicine was built to be the safety net. But a safety net works because it catches the exceptions. If dozens of people are falling off the tightrope, that's no longer a safety net. That's just how you get down…But while the people inside healthcare keep compensating for what doesn't work, the structures around them have remarkably little reason to change.”
Emerson Floyd retweeted

Fucking brutal


Thanks to Terry Tao for featuring me on his blog!
terrytao.wordpress.com/2026/…

Emerson Floyd retweeted

@Frances98392343 @Ecgloverr @ecgrhythms @ecgandrhythmRoe @smithECGBlog @PendellM 55y m smoker, 10/10 pain for an hour, came in by car

Emerson Floyd retweeted

You can’t really diagnose either using a single lead in monitoring mode. You need a diagnostic quality ECG.
The issue is that filters distort the ST segment.

Emerson Floyd retweeted

The most stressful part of what we (ICs and CT surgeons) do every day is not the heroic Hail Mary cases (that we often “humbly” discuss) but the routine stuff that goes south. Congratulations on your courage to publicly share. I hope in the end your patient had a good outcome.

CathLab Nightmare:
Female, 70yo, NSTEMI. MidLAD culprit lesion.
When I injected the last one at RCA to begin LAD PCI, this happened…
@FurquimThyago @nicedoc @Hragy @DFCapodanno @djc795 @gbiondizoccai @CMichaelGibson @DrMarthaGulati @KPujdak @sbrugaletta @adrianocaixeta
Emerson Floyd retweeted

🫀SEPTUM ACTIVATION 🫀
Let's not forget that the septum depolarizes in both directions.
Each ventricle has its own activation wavefront.
LV: left ➡️ right
RV: right ➡️ left


Emerson Floyd retweeted
PACs illuminate so many electrophysiological phenomena in this tracing. One could write a book chapter. #ECG #Cardiology #EPeeps

Emerson Floyd retweeted

So, an oligarch who controls major Russian gambling and automotive assets paid a six figure sum for a post-wedding party in the Bahamas as a gift to the son and daughter-in-law of the President of the United States. Do I have that right? If so, do the President and his family not see how bad this looks? Republicans (I'm one) would be up in arms if a gift like this were accepted by the immediate family of a Democrat serving as President of the United States. Even if we were to accept for the sake of argument the unlikely proposition that Umar Krelev is not buying influence, the appearance of impropriety is glaring. Is there no one in or near the President's family who will say, "no, this kind of thing is not appropriate--we'll pay for our own post-wedding party"?
Emerson Floyd retweeted
New IBCC chapter on CT scan for patients with a history of contrast allergy 😁
Some key points:
☢️ If contrasted CT is emergently necessary (e.g. stroke, trauma) just get it. Full stop.
☢️ If the contrast allergy reaction occurred before 2000 it's likely due to oudated high-osmolal contrast dye. You don't need to worry about this, just get the scan. (Canadian guidelines)
☢️ Define the severity of the prior reaction. Unless it was *severe* and resembling an allergy (e.g. anaphylaxis, vital sign abnormalities) you don't need to really worry about it.
☢️ Antihistamines *do* probably reduce the risk of mild contrast reactions (e.g., urticaria). If you want to give a dose of oral nonsedating antihistamine that's fine (eg cetirizine 10 mg PO). Antihistamines don't save lives or prevent anaphylaxis. And you don't need to give a big bomb of IV diphenhydramine.
☢️ The best available data suggests that pre-scan steroids don't prevent severe reactions. Canadian guidelines say not to give steroids. Historically the American Allergy guidelines have also recommended not giving steroid. The most recent American College of Radiology plus American Allergy consortium guidelines (below) say to "consider" steroid (figure below). That means exercise your best judgement about risks vs benefits.
☢️ If you do decide to give steroid you can give a single dose of 200 mg IV hydrocortisone or 40 mg IV methylprednisolone 4-8 hours before the CT scan. You don't need to give multiple doses of steroid. You don't need to wait a billion hours before the scan. Hydrocortisone probably makes the most pharmacokinetic sense because it's relatively short-acting and has low CNS penetration (less delirium).
☢️ Changing to a different formulation of contrast dye DOES probably help *if* you can get this done. Unfortunately patients often don't know what type of contrast dye they received previously. Also, most hospitals only have access to a couple types of contrast dye. So this works better in theory than reality.
☢️ No matter what you do there is always a nonzero risk that the patient may develop anaphylaxis after CT scan. This should be treated aggressively with epinephrine per usual. There's no way to get the patient to zero risk. Trying to get to a zero-risk situation will actually cause delays and harm.
#1/2 (link in next post)


Emerson Floyd retweeted

New from @jem_journal : Diagnostic dilemma: acute aortic syndrome vs acute coronary occlusion in the emergency department
jem-journal.com/article/S073…

Emerson Floyd retweeted

Reminder:
If you perform 100 medical procedures that 1% complication rate catches up with you
Stay humble, continue to learn
#foamed
#foamcc

Emerson Floyd retweeted

Large D1 Culprit
Ostial thrombotic lesion
TIMI 1 flow
Subtle 🇿🇦 flag sign!


Emerson Floyd retweeted

Perfect example of execs cutting staff to turn a profit while our patients suffer: @CommonSpirit is laying off critical support staff at St. Joseph's Medical Center.
When we asked who would cover the work, management said "the nurses will do it." 😡
nationalnursesunited.org/pre…

Emerson Floyd retweeted
My 2 cents on research during medical school & residency:
Research success is easy to metric (20 articles!!) and communicate on the CV in a highly visible way.
Mastering clinical medicine is nearly impossible to metric or report accurately on a CV.
The inevitable result = students & trainees are pushed to focus on research (at the cost of spending less time learning clinical medicine).
This is a major problem. For most trainees and students, skimping on clinical knowledge while mastering the dark art of publishing scientific articles won't serve them well in the long run.

Dr. Glaucomaflecken continues his fight against med student research (see link). I don't think we necessarily have to ban research, although that would be an improvement. We just need program directors to recognize that ranking by research pubs is bad for our profession. It causes early burnout among trainees and cheapens the value of research. Spread the word about the downsides of research rankings. There are lots of excellent program directors who will respond to this message the more it gets out. facebook.com/share/r/1EcmykH…