
Emergency Physician - East Texas, Tour Medical Dir - Houston, Dallas Symphonies, Ex-Regional Director Envision, Juilliard-trained Violinist, Medical AI
Lufkin, TX
Joined January 2016
- Tweets3.5K
- Following2.4K
- Followers2.5K
- Likes12K







MUMPS was written at Massachusetts General Hospital 60 years ago. It still runs under some of the largest record systems in medicine. This series asked whether a modern language would serve us better in building and maintaining records that are safe, effective, and efficient.
I could not find a single study that compares MUMPS with a modern alternative on safety, defects, cost, or speed.
The money I could document comes to about $90 billion. Epic, which keeps its charts on a descendant of MUMPS, took in $32 billion from 2019 through 2025. The VA reported $2.3 billion to run VistA from 2015 to 2017. Replacing the three federal MUMPS records carries about $56 billion in estimates and contracts, $48 billion of it the VA's.
The evidence that does exist points in different directions. Epic was KLAS's top-rated record for large and midsize hospitals in 2026. VistA was up 99.9967 percent of the time in 2022, by figures cited at a House hearing. GAO says the VA is replacing it because it is technically complex, costly to maintain, and limited in sharing data. About 70 percent of the VA's MUMPS developers were eligible to retire in 2023. In a 2018 study, the same X-ray order took emergency physicians an average of 64 seconds and 31 clicks at one health system and 24 seconds and 8 clicks at another on the same vendor's record.
None of it isolates the language.
In medicine, we must prove small things to get funded. A new drug needs trials. A new device needs data. For the foundation under all that money, I found none.

How the $90 billion adds up, documented pieces only. Epic revenue: $32.2 billion for 2019 through 2025, as reported by Becker's Hospital Review (Epic is private). VistA: $2.3 billion for fiscal 2015 to 2017 as reported by the VA; GAO found only about $1 billion of it documented (GAO-19-679T). Replacing VistA, CHCS, and RPMS: about $48 billion, the VA's own estimate (Military Times, Sept. 3, 2026); $5.5 billion, the Defense contract award total (GAO-22-104521); up to $2.54 billion, the IHS 10-year contract. Not counted: hospitals' own staff and hardware, Epic before 2019, other VistA years, InterSystems licenses, MEDITECH, and systems abroad.
Not found by three frontier AI passes or the source check: an independent, modern benchmark of MUMPS platforms against other databases on a health record workload, or a controlled study of a language effect on defects, security, cost, or harm.
Other sources: KLAS 2026 Best in KLAS; House VistA hearing, March 7, 2023; GAO-23-106685; Ratwani et al., JAMIA 2018, doi.org/10.1093/jamia/ocy088
Part 6 of 6 in a series on MUMPS and what AI means for the code under our EHRs.

Epic pointed AI at its own code this year. The AI found security flaws its developers had missed.
On Aug. 18, Epic's security chief, Stirling Martin, said the company is a heavy user of Mythos, a restricted Anthropic model. "Despite a codebase that is several 100 million lines large, AI models can easily make observations that our expert developers can't see."
On Sept. 22, CEO Judy Faulkner said Epic was pausing most technology development for another six weeks to focus on security.
Martin later told The New York Times that some MyChart setups could let outsiders view patient records without the access appearing in the logs. I have not found a public description of the flaws, or a report that anyone used them.
Epic's languages include Caché, InterSystems' MUMPS platform. The reports do not say which language held the flaws.
Martin also told customers that patching within 30 days is no longer good enough.

Sources. Martin's Aug. 18 remarks: Becker's Hospital Review, Aug. 21, 2026 (Giles Bruce), and Fierce Healthcare, Sept. 23, 2026 (Heather Landi), which also reports Faulkner's Sept. 22 remarks. MyChart and the logs: Martin to The New York Times, Sept. 30, 2026, as reported by TechCrunch, Oct. 2, 2026 (Zack Whittaker): techcrunch.com/2026/10/02/me…
Languages: Epic's careers page. Mythos: Anthropic's Project Glasswing page (launched April 7, 2026), which says Anthropic does not plan to make the model generally available, and its June 2, 2026 expansion to healthcare.
Per TechCrunch, the model did not say whether the flaws could be used to alter records without detection. An Epic spokesperson told Fierce the development roadmap had not changed. Epic says it "does not have access" to customers' medical data.
Part 5 of a series on MUMPS and what AI means for the code under our EHRs.
Series drafted with Opus 5.5 Max with assist from Grok Heavy, 6.1-SOL, and Gemini 4 Argon.

AI models now read MUMPS well enough to document it.
In 2024, MITRE tested four models on 5,107 lines of VistA's code. Their comments were "highly readable and factual." In early trials, the models "would often alter the code to generate documentation."
In August, InterSystems tested 14 models on 140 tasks in ObjectScript, its descendant of MUMPS, one try per task. Scores ran from 0.515 to 0.851.
In September, it put models inside coding agents that compile and run their own code. DeepSeek V4 Flash scored 0.807 alone and 0.936 to 1.000 in eight agent setups.
InterSystems wrote, ran, and graded both tests.
Before these models, from 2005 to 2014, a contractor, TSRI, converted parts of VistA and the Defense Department's CHCS to Java and reported that "The translated code ran identically to the original code." Both agencies later chose Cerner.
I have not found a MUMPS test like OpenAI's Oct. 19 COBOL test, where every output must match the original exactly.
By the end of 2027, I expect one.

Sources. MITRE: Diggs et al., "Leveraging LLMs for Legacy Code Modernization," arXiv 2411.14971, Nov. 2024. InterSystems ObjectScript LLM Benchmark, run Aug. 17, 2026: github.com/intersystems-comm…
Nicholai Mitchko, ObjectScript Agent Bench, InterSystems Developer Community, Sept. 2, 2026. TSRI's own case studies. OpenAI, "Advancing coding in low-resource programming languages," Oct. 19, 2026.
In September, each setup got one try per task, run-to-run variance was not measured, and InterSystems says those scores "are not comparable to the first article." The 0.936 comes from its results table; its text gives DeepSeek V4 Flash 0.957 to 1.000.
Where this could be wrong: no MUMPS or ObjectScript migration test that requires identical output is published by Dec. 31, 2027.
Part 4 of a series on MUMPS and what AI means for the code under our EHRs.

The VA, the Defense Department, and the Indian Health Service each ran a health record built on MUMPS. All three chose the same replacement: Oracle Health, the former Cerner.
Defense signed in July 2015. Its last site went live in March 2024.
The VA signed in 2018. Seventeen VA sites run the new record, and Anchorage and Cleveland were scheduled for Oct. 24. The plan reaches all 170 medical centers in November 2031.
In August, the VA raised the contract ceiling from $10 billion to over $27 billion. Its own estimate to deploy and sustain the system: about $48 billion.
In 2024, the VA's pharmacy and patient safety leaders told its inspector general the new record "is fundamentally unsafe."
The Indian Health Service went live at its first three sites on Sept. 26.
The VA plans 26 more sites in 2027. I expect fewer.

Sources. Defense: Healthcare IT News on the July 29, 2015 award; health.mil on the last go-live, March 9, 2024. VA: Rep. Maxine Dexter's release, Sept. 2, 2026, on the ceiling; Military Times, Sept. 3, 2026, on the VA's estimate, the 2018 deal, and the 2026 and 2027 schedules: militarytimes.com/news/penta…
VA OIG report 23-01450-114, March 21, 2024. IHS: Nov. 8, 2023 selection of GDIT with Oracle Cerner technology to replace RPMS; Oct. 13, 2026 go-live release.
The $27 billion is a contract ceiling. The $48 billion is the VA's estimate for deployment through 2031 plus sustainment, and Deputy Secretary Paul Lawrence acknowledged it was not independent. Seventeen counts the six original sites plus 11 in 2026.
Where this could be wrong: the VA completes 26 or more site deployments in 2027. Basis for my call: 13 scheduled in 2026, half the 2027 plan.
Part 3 of a series on MUMPS and what AI means for the code under our EHRs.

About 70 percent of the VA's MUMPS developers were eligible to retire, a VA official told Congress in March 2023.
"MUMPS is not taught in computer science classes, and the pool of MUMPS programmers shrinks every year as they retire," said Daniel McCune, then the VA's executive director of software product management.
Rep. Matt Rosendale, then the subcommittee chairman, pushed back: "the numbers do not bear that out." In 2022, 1,129 full-time equivalents worked on VistA, the VA's MUMPS-based record system. Ten years earlier, 1,134.
McCune's reply: the VA's employees "have stayed long beyond what a typical workforce would stay."
The 70 percent "has been creeping up year over year."
Asked when the VA would last use VistA, he called it "an interim solution for an indefinite amount of time."
The VA's current schedule puts the new record system in all 170 medical centers by November 2031.
"Eventually we are going to start to lose them."

Sources. House Veterans' Affairs Subcommittee on Technology Modernization, VistA hearing, March 7, 2023, Serial No. 118-2, printed record of the spoken testimony: congress.gov/118/chrg/CHRG-1…
VA EHR deployment schedule, updated Sept 15, 2026: digital.va.gov/ehr-moderniza…
The 70 percent covers the VA's own MUMPS developers as of March 2023. The FTE counts cover everyone who worked on VistA.
Other witnesses saw it differently. Roger Baker, the VA's former CIO: "Even in saying MUMPS, what you are really saying is expertise about VistA as a large-scale application." Peter Levin of Amida Technology Solutions: "The single biggest problem with VistA, at least in my opinion, has nothing to do with MUMPS or the availability of language competencies of any individual programmer."
I could not find a published count of MUMPS programmers anywhere. If you know of one, I would like to see it.
Part 2 of a series on MUMPS and what AI means for the code under our EHRs.
Mass General keeps its charts on a descendant of a programming language its own lab wrote in 1966.
The language is MUMPS, the MGH Utility Multi-Programming System. Neil Pappalardo, Robert Greenes, and Curt Marble built it in Octo Barnett's lab to manage patient records.
Epic's core database runs on InterSystems' Caché, now moving to IRIS. Both descend from MUMPS. Epic's careers page still lists Caché in its stack.
Mass General moved to Epic in 2016.
The VA's VistA held more than 15 million lines of MUMPS, by the VA's own count in 2010.
The Indian Health Service: "The core of RPMS is written in MUMPS," a 2019 HHS assessment found.
The Defense Department's old record system started as a fork of VistA.
InterSystems says its technology touches the health records of 2 out of 3 Americans.
Pappalardo went on to found MEDITECH in 1969. He died in January, at 83.

Sources. Greenes, Pappalardo, Marble, Barnett, Computers and Biomedical Research 1969;2(5):469-485 (MUMPS, developed 1966 to 1967).
NetApp, Epic architecture, Oct 2024: Chronicles moving from InterSystems Caché to IRIS. Epic careers page, accessed Oct 22, 2026.
Forbes, March 4, 2013: Epic and InterSystems "are rooted in an older programming language called MUMPS."
VA CIO Roger Baker, Aug 26, 2010, via Nextgov. HHS/IHS legacy assessment, May 14, 2019. InterSystems federal capability statement. MEDITECH, Jan 30, 2026. Boston Globe, April 5, 2016.
"Touches" is InterSystems' own word and figure. Epic has not published how much of its code is M. Today's platforms, InterSystems IRIS among them, are actively developed and run Python alongside M.
Part 1 of a series on MUMPS and what AI means for the code under our EHRs.
Drafted with Opus 5.5 Max based on input by Astra 6, Argon 4, and Grok-Heavy
Your hospital's traditional Medicare claims still run on COBOL and IBM mainframes.
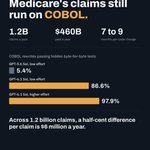
That's from a CMS planning document. The four systems behind Original Medicare's fee-for-service claims, about 1.2 billion claims and $460 billion a year, "run on COBOL, Assembler Language Code (ALC), and IBM mainframes."
This week OpenAI reported that its newest model can translate COBOL into modern languages and pass hidden tests that demand byte-for-byte identical output.
At the same low setting, success went from 5.4 percent with GPT-5.6 Sol to 86.6 percent with GPT-6.1 Sol, at 61 percent of the cost. At higher effort, 97.9 percent.
Why should doctors and administrators care?
The rules that decide what gets paid live inside that code. CMS says a change takes a 7 to 9 month code cycle today.
Its replacement program, ClaimsCore, aims for hours or days. A proof of concept runs through January 1.
The hard part of these migrations is arithmetic. OpenAI's example: COBOL drops extra decimal digits unless told to round. A rewrite that rounds instead runs without errors and pays different amounts.
Across 1.2 billion claims, a half-cent difference per claim is $6 million a year.
Code migration has a mechanical check: run the old and new versions and compare the output. Models climb fastest on tasks with checks like that.
Billing code can be checked that way. Bedside medicine is checked by patient outcomes, which take years.
The clinical side has its own 1960s language. Epic and the VA's VistA are built on MUMPS, developed at Massachusetts General Hospital in 1966 and 1967.
OpenAI did not test MUMPS. If it follows COBOL, the cost of leaving an EHR falls with it.
My prediction: by the end of 2027, a ClaimsCore vendor says publicly that it used AI to pull Medicare's payment rules out of the COBOL.

Sources. OpenAI, Oct 19, 2026: openai.com/index/low-resourc…
CMS ClaimsCore statement of objectives, a pre-decisional draft published by Washington Technology, June 2026: washingtontechnology.com/med…
MUMPS: Pappalardo, Greenes, and Marble, Massachusetts General Hospital.
OpenAI does not publish the test set or program count, and gives no high-effort score for GPT-5.6 Sol, so the clean comparison is at low effort. OpenAI says production use "still requires expert review and testing against the system's business rules and dependencies." The CMS dates are from a draft and may move. The half cent is an illustration. OpenAI did not test MUMPS.
Where this could be wrong: if Medicare's payment rules live mostly outside the code, in manuals and contractor edits, migration speed stops being the bottleneck.
Drafted Argon 4 and Opus 5.5 Max

We physicians keep telling ourselves that patients trust us, and only us, for medical care.
They do, for now. We hold the keys to the kingdom: the knowledge, the skills, the prescription pad. And patients were taught to trust us.
So to a large extent, it's historical programming and necessity.
That trust is already slipping. In a 50-state survey of more than 443,000 adults, trust in physicians and hospitals fell from 71.5 percent in April 2020 to 40.1 percent in January 2024. More than 300 million people a week now ask ChatGPT health questions.
Take hypertension. We don't manage it particularly well: 33.2 million Americans on treatment are still above goal.
When AI is shown to manage blood pressure as well as the top 1 percent of physicians, 24/7, on an iPhone, for about $1 a visit, patients will drop their doctors like a hotcake.
This will shock a lot of people. Especially physicians.

Sources. Perlis et al., JAMA Network Open, July 31, 2024: 24 online surveys, 443,455 US adults, April 2020 to January 2024. OpenAI, Health in ChatGPT, July 23, 2026: openai.com/index/health-in-c…
Million Hearts, NHANES 2017 to 2020: millionhearts.hhs.gov/data-r…
The 33.2 million are treated adults still at or above 130/80. That figure reflects adherence and access as well as prescribing.
The hypertension threshold is the one I mean. If an AI has already met it, send me the study.

@VinGuptaMD gave a talk today on holding back technology that is 90% accurate at diagnosing undiagnosed high blood pressure because many doctors insist on 100%. The cost of non-deployment across a large society is high.
This neglects that even if diagnosed, 50% or more of patients under a doctor's care never get it controlled.
That will change with AI.
@ED_WCMC @OpenEvidence @TravisZack2
Cornell Telehealth AI conference today was a huge success
Travis Zack, CMO of OE headlined:
Doctors ask OpenEvidence about treatment more than twice as often as they ask about diagnosis.
JAMA published the numbers last week: 271 million OpenEvidence queries from more than 950,000 US clinicians over two and a half years.
Treatment and management: 33.1 percent of physician queries. Diagnosis: 13.9 percent.
Monthly active users went from 355 in January 2024 to more than 703,000 in June 2026.
In 2026, about 90 percent of clinicians active in one month came back the next.
Use ran highest among early-career physicians, and physicians often asked about fields outside their own.
A JAMA review of 519 LLM studies from 2022 to early 2024: 19.5 percent tested diagnosis, 9.2 percent treatment recommendations, 0.2 percent writing prescriptions. Only 5 percent used real patient data.
In use, treatment outnumbers diagnosis more than 2 to 1. In the studies, diagnosis outnumbered treatment 2 to 1.
Treatment advice fails mostly by leaving things out. In NOHARM, which graded management advice on real eConsults, 76.6 percent of severe errors were omissions.
The JAMA editors noted the study did not evaluate answer quality or effects on patient care.
I heard OpenEvidence's chief medical officer, Travis Zack, at Weill Cornell today. He opened with his own challenging-to-diagnose red eyes.
Two virtual visits and OpenEvidence all missed it, because he never mentioned the rash from his wedding ring. Nickel allergy.
His line: "No reasoning system is gonna be good enough without that right input information."
My prediction: by the end of 2027, a peer-reviewed study links clinicians' AI evidence queries to their patients' outcomes.
More from Zack's talk:
OpenEvidence now gets about 1.9 million questions a day from US clinicians alone.
Each question starts from about 40 million sources, narrowed to 150 to 250, then to the 5 to 15 it cites. The ranking weighs relevance, recency, strength of evidence, and authority. His hard case: a newer observational paper against an older RCT.
Sources update every 24 hours. The system has no open internet access.
"The easy questions are answered by abstract. The real questions in medicine are answered by the full text." NEJM was the first full-text license, and OpenEvidence had to prove it could reproduce their papers faithfully.
On standards: "You have to be right, and you have to be right for the right reasons, and you have to be able to justify why those reasons are right."
Growth came from trainees, with no marketing. Heaviest users: internal medicine, family medicine, infectious disease, oncology. Lightest: radiology and orthopedics.
Emergency medicine runs a little heavier on diagnosis. Evidence questions come from 6 a.m. to midnight. After midnight, procedures and documentation. Outpatient specialists read after clinic.
Knowledge expires faster now. Lung cancer is a dozen or more subtypes, and he said what you learn can be outdated in three months.
Physician AI use: 38 percent in 2023, 81 percent now. He thinks that undercounts, because many people use AI without knowing it.
His description of language models: "statistics with style."
UpToDate is coming to Doximity's AI.
In the coming weeks, clinicians at health systems that use both will see an UpToDate answer next to Doximity Ask's AI answer.
NEJM Group signed with OpenEvidence in February 2025.
UpToDate signed with Suki in March 2025.
The JAMA Network signed with OpenEvidence in June 2025.
Wiley signed with OpenEvidence in March 2026, Cochrane included. Two days later, UpToDate signed with Microsoft for Dragon Copilot, Microsoft 365 Copilot, and Teams.
Now UpToDate and Doximity. At least six content deals in 20 months.
So what changes for the physician holding the phone?
Two answers on one screen. One generated by Ask. One drawn from UpToDate's 13,000 topics, reviewed by more than 7,600 expert clinicians, editors, and peer reviewers.
Doximity's CEO, Jeff Tangney: "Doctors know the value of a second opinion."
When they disagree, the physician decides which one to follow.
NOHARM, the Stanford and Harvard safety study, randomized 101 generalist physicians. AI assistance improved their performance over conventional resources. But the AI-assisted physicians "frequently omitted valuable AI-generated recommendations" and still trailed many AI systems working alone.
The same study found diverse multi-agent setups had 5.9x higher odds of top-quartile safety. Safety is a committee. That points to a second model flagging the disagreements, so the physician does not have to find them.
Doximity says more than 12,000 "cited physician experts" already evaluate Ask's outputs through PeerCheck. The numbers I want from Doximity and Wolters Kluwer: how often the two answers disagree, on which topics, and which one physicians follow.
Two physicians in the same ED, one in OpenEvidence and one in Ask, are now drawing on different licensed content.
OpenEvidence licenses NEJM, JAMA, and Cochrane. Wiley's release describes it as trusted by more than 40 percent of U.S. physicians. Ask will show UpToDate.
Access depends on the hospital. Doximity says its clinical AI suite is at more than 165 health systems, including 10 of the nation's top 20 hospitals. The UpToDate answer goes to the ones that also use UpToDate.
My prediction: by April 30, 2027, another AI tool for clinicians announces a deal to put UpToDate, DynaMed, or BMJ Best Practice inside its answers.

Two of the resources physicians reach for most have lived in separate tabs. That's about to change.
We've partnered with @WoltersKluwer to bring @UpToDate's expert-reviewed content into Doximity Ask.

Sources. Doximity, Amit Phull, MD, Oct 20, 2026: blog.doximity.com/articles/d…
NOHARM, arXiv v4, July 13, 2026: arxiv.org/abs/2512.01241
OpenEvidence and NEJM Group, Feb 19, 2025. Wolters Kluwer and Suki, Mar 3, 2025. OpenEvidence and the JAMA Network, Jun 5, 2025. Wiley and OpenEvidence, Mar 3, 2026. Wolters Kluwer and Microsoft, Mar 5, 2026.
NOHARM used eConsult cases. The second-model flagging line is my inference from its results.
The announcement does not give pricing, whether the UpToDate answer is AI-generated or excerpted, or what Ask does when the two answers disagree.
The prediction counts any AI assistant, scribe, or search tool for clinicians, announced by either party.
Where this could be wrong: if Ask merges the two answers into one, the disagreement stops being visible.
Drafted with Claude Opus 5.5 Max
