

Cholesterol and dietary fat research. Author of "The LDL Scam" - https://teapaw.org/t.co/LgoIxPfrrC
Joined April 2019
- Tweets4.5K
- Following1.2K
- Followers1.9K
- Likes13.2K






Pinned Tweet
My first blog post 👇
ApoB: An Overrated Marker of Risk - buymeacoffee.com/DietaryDiar…

Great timing!
Here is my new post on Ference et al. (2017) 👇
"Pseudoscience in the Literature: The Ference Graph"
buymeacoffee.com/dietarydiar…


So he read it wrong the first time, or he's reading it wrong now.
I think it's the latter.
The paper he cites first:
“Ference et al., 2017 — “Low-density lipoproteins cause atherosclerotic cardiovascular disease”
About which he says:
“This is probably the single best paper for the intellectual foundation of my reversal.”
I've called this paper a fraud in the past.
I still think it's the case. I'm not the only one. @zoeharcombe wrote a nice analysis of the problems with this paper here:
zoeharcombe.com/2026/06/does…
With part 2 here:
zoeharcombe.com/2026/06/does…
Next he mentions:
“Borén et al., 2020”
One of my favorites.
It makes the case that ApoB is not causal, but only if you spend a lot of time going through and understanding the references.
My favorite example is their discussion of ‘aggregated’ LDL, which they claim, correctly, is dangerous. They don't mention it in the paper, but one of their references shows that LDL only aggregates when it contains linoleic acid. Remove that, LDL is protected from aggregation.
I don't think carnivore is enough to protect people from CVD or chronic disease.
You're not necessarily removing the cause, if you're eating industrially-fed animals like chicken and pork.
This is not a compelling post for me.
They didn't even die less of CVD 🤪
CVD death rates were low but identical between the groups: HR = 1.00 (0.72–1.37).

Assuming they died less of ASCVD @drpablocorral, what did they die of more to result in no all-cause mortality benefit?
New post 👇
The Physiologically Relevant LDL Range is 20–40 mg/dL?
buymeacoffee.com/dietarydiar…

At what point do we realize that these people are just making up numbers?
Is it 35-50 mg/dL? 20-40 mg/dL? 50-70 mg/dL? (Various ranges I've seen in the literature.)
I'm confused 🤪

If everybody had low LDL cholesterol (between 35-50 mg/dL) for their whole life, there may be no more heart attacks.
Dr. Sek Kathiresan (@skathire), CEO at Verve Therapeutics and head of obesity research at Eli Lilly, explains:
ZahcM retweeted

📌Multiple hypotheses have been proffered over the years
💌"WSS is the ONLY evidence-based atherogenic risk factor identified that meets or approaches the definition of “SUFFICIENT” and “NECESSARY,” and has a reasonable potential to fulfill the criteria for CAUSATION"

Mortality in FOURIER Participants With Diabetes: A Regulatory-Data Reanalysis of Evolocumab Outcomes
dom-pubs.pericles-prod.liter…


Restoring mortality data in the FOURIER cardiovascular outcomes trial of evolocumab in patients with cardiovascular disease: a reanalysis based on regulatory data - bmjopen.bmj.com/content/12/1…
"In the meantime, clinicians should be sceptical about prescribing evolocumab . . ."


Correct. Leaving aside the dubious data from these marketing trials funded by criminals, a standard random-effects model would not show statistically significant associations with total mortality (or cardiac mortality).

Agreed. I find the injury hypothesis (whether it be damage to the intima, media or adventitia) to be far more convincing than the retention hypothesis.
I discussed the topic in my recent ebook!
buymeacoffee.com/dietarydiar…

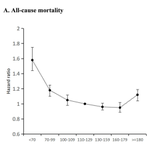
"Notably, very low cholesterol levels (i.e. TC<130 mg/dL or LDL-C<70 mg/ dL) correlated with a 3–9-year reduction in lifespan and up to a 2-fold increase in mortality risk."
jogh.org/2026/jogh-16-04025


Case report:
"We report the case of a 35-year-old African American woman with recurrent chest pain . . . Despite intensive lipid-lowering therapy and optimal LDL-C levels, coronary disease progression was observed."
sciencedirect.com/science/ar…

"Higher levels of ApoB, LDL-C, and total cholesterol were consistently associated with lower depression risk, supporting a protective role."
frontiersin.org/journals/nut…

"In conclusion, our findings identify ox-HDL-C, ox-LDL-C, and ox-Lp(a) as independent predictors of MACEs in patients with T2DM and coexisting CHD."
Also, ApoB and LDL-C were not associated with increased atherosclerotic burden.
e-dmj.org/journal/view.php?d…

New post 👇
"The New Saturated Fat Meta-Analysis (Steen et al.)"
buymeacoffee.com/dietarydiar…

Finally made the time to examine this paper!
@jheilesonPhD
teapaw.org/ZahcM/status/200101334…
High Dietary Linoleic Acid Intake Suppresses Eicosapentaenoic Acid Status and Shifts Oxylipin Metabolism Towards Arachidonic Acid in Healthy Adults: A Randomized Controlled Trial - medrxiv.org/content/10.64898…
Short-term trial, but nice effort!
@TuckerGoodrich

Often overlooked, but the opposite is also true. If we put a coronary artery to do the job of a vein or observe a coronary artery under lower blood pressures (anomalous arteries), atherosclerosis in the artery would be minimal or absent.
@xinggang_wang

Your veins and arteries carry the same blood. Same LDL. Same ApoB. Same everything. Yet veins almost never get plaque. Arteries constantly do.
Maybe you've seen the recent discussions about this. It's an interesting question that provides clues in cardiovascular science, and could challenge how we think about LDL and ApoB. 🧵
Yep. A poorly conducted trial that says nothing about LDL per se (composite endpoint as primary, nonblinded, mixing different drugs and doses with various pleiotropic effects, etc.).
Also, in the fine print: 31 deaths (2%) in the intensive group vs. 29 (1.9%) in conventional.
The (ab)use of food frequency questionnaire data in substitution modelling - nature.com/articles/s41430-0…
"The majority of substitution modelling analyses that relied on FFQ data had not adequately addressed fundamental limitations in measurement accuracy."

